
Volume 23, Issue 2 (6-2026)
J Res Dev Nurs Midw 2026, 23(2): 50-56 |
Back to browse issues page


Download citation:
BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:


BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:
Moghimian Shahrbabaki R, Arya S, Khoshnood Z, Soltaninejad N, Nematollahi M. Effect of white noise on physiological parameters and pain levels during airway suctioning in preterm infants admitted to a neonatal intensive care unit: A Randomized Clinical Trial. J Res Dev Nurs Midw 2026; 23 (2) :50-56
URL: http://nmj.goums.ac.ir/article-1-2202-en.html
URL: http://nmj.goums.ac.ir/article-1-2202-en.html
Reihane Moghimian Shahrbabaki1 

 , Saide Arya1 , Zohreh Khoshnood2 , Najmeh Soltaninejad3 , Monirsadat Nematollahi4
1- Reproductive and Family Health Research Center, Kerman University of Medical Sciences, Kerman, Iran
2- Nursing Research Center, Kerman University of Medical Sciences, Kerman, Iran
3- Department of Pediatrics, School of Medicine, Afzalipour Hospital, Kerman University of Medical Sciences, Kerman, Iran
4- Reproductive and Family Health Research Center, Kerman University of Medical Sciences, Kerman, Iran ,monirnematollahi@yahoo.com
2- Nursing Research Center, Kerman University of Medical Sciences, Kerman, Iran
3- Department of Pediatrics, School of Medicine, Afzalipour Hospital, Kerman University of Medical Sciences, Kerman, Iran
4- Reproductive and Family Health Research Center, Kerman University of Medical Sciences, Kerman, Iran ,
Full-Text [PDF 507 kb]
(368 Downloads)
| Abstract (HTML) (2453 Views)
Discussion
This study investigated the effects of white noise on pain levels and physiological parameters in premature infants during airway suctioning. The findings demonstrated that white noise was effective in alleviating pain during airway suctioning in premature infants.
Consistent with the present findings, Taplak (2021) conducted a study of 80 infants to evaluate the effects of breast-milk odor, white noise, and the fetal position on pain during airway suctioning. The results indicated that both white noise and the fetal position before intratracheal suctioning significantly reduced pain (24). That study evaluated the effect of white noise on pain during tracheostomy suctioning in infants, similar to the present investigation. However, it used the PIPP tool to measure pain, which differed from the instrument used in the present study.
Although routine suctioning is not recommended in the NICU, it may be necessary in emergencies. Studies indicate that suctioning is both unavoidable and uncomfortable (6). Pekygit (2023) studied 90 infants to examine the effects of white noise and the fetal position on pain during heel sampling. Infants who received a combination of white noise and fetal-position interventions experienced significantly less pain than those in the other two groups (25). That study focused on term infants and evaluated the effectiveness of combining two non-pharmacological interventions, namely white noise and the fetal position, to alleviate infant pain. This approach differed from that used in the current study. Further research is needed to evaluate the effectiveness of combined non-pharmacological interventions in this area.
In a study of 66 infants, Ren (2022) found that white noise did not positively affect cortical pain responses, pain scores, or behavioral and physiological parameters in infants experiencing pain (21). This finding contradicts the results of the current study. One possible explanation for this discrepancy is the difference in study populations: the previous study examined term infants, whereas the current study examined preterm infants. Furthermore, the white noise used in the present study differed substantially from that used in the previous study. Specifically, the previous study used music as white noise, whereas the current study used sounds generated from the uterus and heartbeat. Kucukoglu (2016) examined the effect of white noise on vaccination pain in premature infants and found that the intervention group experienced significantly lower pain levels. In that study, an MP3 player was used to emit white noise, whereas in the present study, infants wore headphones set to 45 dB (18). The duration and type of auditory stimulus used to generate white noise also differed considerably from those in the present investigation. Nevertheless, headphones may be more advantageous for evaluating the effect of sound on infants because they provide more comprehensive auditory coverage.
Consistent with the study’s second objective, which was to examine the effect of white noise on physiological parameters in premature infants, the findings showed beneficial effects on heart rate and oxygen saturation during airway suctioning. Similarly, Düken (2023) examined the effects of massage and white noise on physiological indicators in premature infants. Premature infants who received massage and were exposed to white noise in the morning and evening for three consecutive days showed significant differences in peak heart rate, respiratory rate, and oxygen saturation compared with the control group. However, no significant differences were observed between the white-noise and massage groups. In agreement with the present findings, white noise was effective in influencing the physiological parameters of premature infants (19). One difference between the two studies was the duration of the white-noise intervention. The intervention lasted three days in the previous study but only approximately 20 minutes in the current study because of the researcher’s time constraints.
Kim and Hye (2023) examined the effect of white noise on heart-rate responses and oxygen saturation during heel sampling in premature infants. Premature infants in the intervention group had a lower heart rate and higher oxygen saturation than those in the control group (17). Various forms of white noise have been used as non-pharmacological pain-relief interventions to evaluate their effects on physiological parameters. These include music, recitation of the Quran (26), heartbeat sounds (19), the mother’s voice (27), and the mother’s lullaby (10). Liao (2021) examined the effects of maternal voice and white noise on the physiological responses of 103 premature infants admitted to the NICU. Infants were exposed to white noise without their mother’s voice for 20 minutes, three times a day, over four consecutive days. The findings showed a significant increase in oxygen saturation. However, no significant differences in salivary cortisol levels or heart rate were observed among the three groups (27). The intervention in that study was longer than that in the current study, and white noise was more effective than the mother’s voice. In the current study, however, the intervention was administered before, during, and after airway suctioning, a painful procedure.
This study was limited by recruitment from a single treatment-teaching center. Additional limitations included the small sample size and the short intervention period imposed by the student’s time constraints. Further multicenter trials are needed to confirm these findings across a broader range of NICU settings and establish the generalizability of the white-noise intervention.
Conclusion
The findings demonstrated that white noise comprising the mother’s heartbeat and uterine sounds affected infants’ blood oxygen levels, heart rates, and pain levels during airway suctioning. Therefore, nurses should consider using white noise as a non-pharmacological pain-relief intervention. Nurses should be aware of the potential effects of this method and seek to implement it in the ward to alleviate pain in infants, who are highly sensitive to painful stimuli. NICU nurses are encouraged to use auditory stimuli, such as white noise, to help reduce the short- and long-term effects of pain in infants.
Acknowledgement
The authors would like to thank all staff members of the neonatal intensive care unit at Afzalipour Hospital in Kerman for their cooperation.
Funding Sources
None.
Ethical Statement
The study was initiated after approval was obtained from the Ethics Committee of Kerman University of Medical Sciences (IR.KMU.REC.1402.147) and registration of the clinical trial (IRCT20221213056807N1). Written informed consent was obtained from the parents of all participating neonates after they had received adequate information regarding the study objectives, procedures, potential risks, and expected benefits. The study was conducted in accordance with the ethical principles of the Declaration of Helsinki. Participation was entirely voluntary, and parents were informed of their right to decline participation or withdraw their neonates from the study at any time without any consequences for their care or benefits. Participant confidentiality was strictly maintained through data coding and anonymization. All study data were stored securely and were accessible only to authorized research personnel.
Conflicts of Interest
The funding organization(s) played no role in the study design; data collection, analysis, or interpretation; or preparation of the report.
Author Contributions
This manuscript resulted from the collaboration of all authors. SA and ZKH designed the study and prepared the study proposal, and NS and SA conducted data collection and analysis. MN and NS analyzed the data, while RM and MN wrote the final draft of the manuscript and prepared the tables. RM submitted the manuscript to the journal. The author(s) read and approved the final manuscript.
Data Availability Statement
The datasets generated and analyzed during the current study are available from the corresponding author upon reasonable request.
Use of Artificial Intelligence
AI was used only for English-language editing, translation assistance, and manuscript proofreading. No AI tools were used for data analysis, interpretation of findings, or generation of scientific conclusions.
Full-Text: (123 Views)
Introduction
Prematurity is defined as birth before 37 weeks of gestation. Preterm infants are often characterized by small size and low birth weight and may require assistance with feeding, breathing, and maintaining body temperature (1-3). On average, these infants undergo 134 painful medical procedures within the first two weeks of hospitalization, with some experiencing more than 3000 such procedures during their NICU stay (4). Recent evidence clearly demonstrates that premature infants not only experience pain but also exhibit heightened sensitivity and stronger responses to painful stimuli (5). In addition, premature infants have a lower pain-tolerance threshold than term infants (4,6,7). The consequences of untreated or inadequately managed pain in preterm neonates are profound and extend beyond immediate distress. Acute pain can cause physiological instability, including increased heart rate and blood pressure, oxygen desaturation, and hormonal stress responses (6). Of greater concern are the potential long-term neurodevelopmental consequences. Chronic or repeated exposure to pain early in life has been associated with altered pain processing later in life, an increased risk of behavioral problems and learning disabilities, and poorer cognitive outcomes (7). Therefore, effective pain management is not merely a matter of comfort but a critical component of optimal neonatal care that is essential for promoting healthy neurodevelopment and mitigating long-term morbidities (5).
Pain-management strategies in neonates include both pharmacological and non-pharmacological approaches. Pharmacological options, such as local anesthetics (e.g., lidocaine) and systemic analgesics (e.g., morphine, fentanyl), are often used during invasive procedures (8). However, these agents carry risks, including respiratory depression, hemodynamic instability, and potential long-term adverse effects. Consequently, non-pharmacological methods are increasingly recognized as important adjunctive or primary interventions, particularly for less invasive or moderately painful procedures. These methods include sucrose administration, swaddling, non-nutritive sucking, kangaroo care (Skin-to-skin contact), and auditory/multisensory interventions (9).
Respiratory disease is a major reason for the admission of premature infants to the NICU (6). Currently, nearly two-thirds of infants born before 29 weeks of gestation require mechanical ventilation at some point during the neonatal period in the NICU (6), owing to transient physiological and clinical factors (10). These patients require endotracheal suctioning to improve oxygen delivery and maintain airway cleanliness and patency. Tracheal suctioning is widely recognized as a common and painful procedure for premature infants. On average, suctioning is performed 4-6 times per day to remove excess secretions and reduce the risk of airway obstruction (6,8). Tracheal-tube suctioning is highly uncomfortable for infants, and the most direct and effective method of alleviating pain caused by repeated tracheal suctioning is to reduce its frequency (6). Therefore, effective pain management during suctioning is essential to minimize infant distress and prevent potential complications (9).
Among non-pharmacological auditory interventions, music and various forms of sound have attracted considerable attention. Although ambient noise in the NICU can be harmful, structured auditory stimuli such as music elicit different responses (11). White noise, defined as sound comprising random frequencies of equal power across the audible spectrum (20Hz to 20 KHz) (12), has demonstrated potential benefits in neonatal populations. It has been shown to improve feeding and sleep patterns and reduce crying duration. Importantly, white noise, particularly when delivered at specific intensities, may mimic the auditory environment of the uterus and thereby provide neonates with a sense of familiarity and security. Exposure to these womb-like sounds and rhythms may induce a calming effect, possibly through familiar sensory input (13).
Despite the heightened sensitivity of premature infants to auditory stimuli, NICU staff attempt to minimize adverse auditory stimuli and persistent noise that may irritate infants (14). However, the effects of music differ from those of ambient noise. Music has a structured organization and typically lacks rapid fluctuations in amplitude, resulting in responses distinct from those produced by noise (11).
White noise comprises all frequencies audible to humans (From 20 Hz to 20 KHz). These frequencies are transmitted randomly and have equal power (12). White noise has positive effects on infants' feeding and sleep patterns and reduces the duration of crying episodes (9). Because of their shared characteristics, white-noise sounds may resemble those experienced by an infant inside the mother's uterus (13). These sounds are influenced by the mother's heart rate, and postpartum exposure to familiar sounds and rhythms may induce a calming effect in the infant (15,16).
Previous studies have explored the effectiveness of auditory interventions, including white noise and womb sounds, in managing procedural pain and promoting neonatal comfort (17-19). Research by Duken et al., 2024 indicated that white noise could reduce physiological indicators of pain in neonates undergoing suctioning (19). However, findings have varied across studies, and inconsistencies remain regarding optimal parameters (e.g., intensity, duration, and type of sound) and the definitive effect on pain scores specifically during endotracheal suctioning in preterm infants.
Despite the growing body of literature, the effectiveness of white noise specifically during endotracheal suctioning in preterm infants, particularly in diverse cultural contexts such as ours, requires further investigation. Based on their experience caring for premature infants in the NICU, the limited use of pain-reduction techniques during airway suctioning, and the scarcity of research examining the effects of white noise during suctioning on pain and neonatal physiological parameters, the research team decided to investigate this issue.
This study aimed to investigate the effect of white noise during endotracheal suctioning on pain intensity and physiological parameters in preterm neonates admitted to the NICU. It was hypothesized that exposure to white noise would reduce pain and improve physiological responses during the procedure.
Methods
This study was a parallel-group, randomized controlled clinical trial using simple random sampling. The study population comprised premature infants hospitalized in the NICU of Afzalipour Hospital in Kerman. The study was conducted between June, 2023 and January, 2024.
Sample size and sampling
Fifty premature infants who met the inclusion criteria and were admitted to the NICU constituted the study sample. Based on a previous study and Coldak's formula, the required sample size was determined to be 44 with 80% power. Consequently, 50 participants were enrolled to allow for a 10% attrition rate (20). The sample size was calculated using [Specify the formula, e.g., the formula for comparing two independent means] based on parameters from a previous study by Zeraati (2018), which reported an effect size relevant to pain scores, with a target power of 80% and an alpha level of 0.05 (20). Reference (18) describes the methodology and findings of this foundational study. Eligible premature infants were selected randomly and assigned to the intervention or control group using a random-number table.
The inclusion criteria were as follows: preterm infants born between 28 and 36 weeks of gestational age; hospitalization in the NICU for a minimum of three days; a fifth-minute Apgar score of 7 or above; absence of congenital abnormalities, such as heart disease or hydrocephalus; no maternal history of alcohol or drug use; absence of diagnosed hearing disorders; absence of acute conditions, such as sepsis, necrotizing enterocolitis, asphyxia, or acute respiratory problems; infant weight greater than 1500 grams; and confirmation of normal hearing by a physician (20). The exclusion criteria were premature death or discharge before the third day; severe responses to auditory stimuli, including screaming, crying, and movement difficulty; and any notable behavioral or physiological changes, such as a decrease in oxygen saturation below 75 or an increase in heart rate above 200 (20).
Eligible neonates were identified through a review of their medical records according to the inclusion criteria. After the parents had been informed about the study, written informed consent was obtained before enrollment.
Allocation concealment was achieved using sequentially numbered, opaque, sealed envelopes (SNOSE). Each envelope contained a card indicating the group assignment (Intervention or control). The envelopes were prepared by an independent researcher who was not involved in patient recruitment or care and were opened by the bedside nurse only after the infant met the eligibility criteria and immediately before the intervention was initiated.
Demographic information and pain measurements were obtained for both groups before, during, and after the intervention.
Because of the nature of the auditory intervention, blinding the infants, parents, and bedside nurses who performed suctioning was not feasible. However, the outcome assessors who administered the pain scales and monitored physiological parameters were blinded to group allocation (Figure 1).
Intervention
In the intervention group, infants requiring suctioning while in the incubator received womb sounds through headphones connected to an MP3 player. Auditory stimulation began 5 minutes before suctioning and continued for 10 minutes after the procedure. The intervention was conducted during the evening shift because the ward was quieter at that time (10). Before the intervention, an audiologist used an audiometer to set the sound intensity to 45 dB (21). Headphones were placed over the infants' ears to attenuate surrounding disturbances while white noise was played. Each infant was continuously supervised by two individuals, a ward nurse and a research colleague, and all infant behaviors were documented. Suctioning was performed only when clinically necessary to improve respiration; no infant underwent suctioning solely for research purposes. Normal saline was not used during suctioning for any participant. Suction pressure followed the standard protocol and ranged from 80 to 100 mmHg (6). Adherence to the neonatal suctioning protocol was ensured, with careful attention to the procedure and associated nursing care for all infants. The researcher completed the pain measurement scale during and after suctioning (10).
Prematurity is defined as birth before 37 weeks of gestation. Preterm infants are often characterized by small size and low birth weight and may require assistance with feeding, breathing, and maintaining body temperature (1-3). On average, these infants undergo 134 painful medical procedures within the first two weeks of hospitalization, with some experiencing more than 3000 such procedures during their NICU stay (4). Recent evidence clearly demonstrates that premature infants not only experience pain but also exhibit heightened sensitivity and stronger responses to painful stimuli (5). In addition, premature infants have a lower pain-tolerance threshold than term infants (4,6,7). The consequences of untreated or inadequately managed pain in preterm neonates are profound and extend beyond immediate distress. Acute pain can cause physiological instability, including increased heart rate and blood pressure, oxygen desaturation, and hormonal stress responses (6). Of greater concern are the potential long-term neurodevelopmental consequences. Chronic or repeated exposure to pain early in life has been associated with altered pain processing later in life, an increased risk of behavioral problems and learning disabilities, and poorer cognitive outcomes (7). Therefore, effective pain management is not merely a matter of comfort but a critical component of optimal neonatal care that is essential for promoting healthy neurodevelopment and mitigating long-term morbidities (5).
Pain-management strategies in neonates include both pharmacological and non-pharmacological approaches. Pharmacological options, such as local anesthetics (e.g., lidocaine) and systemic analgesics (e.g., morphine, fentanyl), are often used during invasive procedures (8). However, these agents carry risks, including respiratory depression, hemodynamic instability, and potential long-term adverse effects. Consequently, non-pharmacological methods are increasingly recognized as important adjunctive or primary interventions, particularly for less invasive or moderately painful procedures. These methods include sucrose administration, swaddling, non-nutritive sucking, kangaroo care (Skin-to-skin contact), and auditory/multisensory interventions (9).
Respiratory disease is a major reason for the admission of premature infants to the NICU (6). Currently, nearly two-thirds of infants born before 29 weeks of gestation require mechanical ventilation at some point during the neonatal period in the NICU (6), owing to transient physiological and clinical factors (10). These patients require endotracheal suctioning to improve oxygen delivery and maintain airway cleanliness and patency. Tracheal suctioning is widely recognized as a common and painful procedure for premature infants. On average, suctioning is performed 4-6 times per day to remove excess secretions and reduce the risk of airway obstruction (6,8). Tracheal-tube suctioning is highly uncomfortable for infants, and the most direct and effective method of alleviating pain caused by repeated tracheal suctioning is to reduce its frequency (6). Therefore, effective pain management during suctioning is essential to minimize infant distress and prevent potential complications (9).
Among non-pharmacological auditory interventions, music and various forms of sound have attracted considerable attention. Although ambient noise in the NICU can be harmful, structured auditory stimuli such as music elicit different responses (11). White noise, defined as sound comprising random frequencies of equal power across the audible spectrum (20Hz to 20 KHz) (12), has demonstrated potential benefits in neonatal populations. It has been shown to improve feeding and sleep patterns and reduce crying duration. Importantly, white noise, particularly when delivered at specific intensities, may mimic the auditory environment of the uterus and thereby provide neonates with a sense of familiarity and security. Exposure to these womb-like sounds and rhythms may induce a calming effect, possibly through familiar sensory input (13).
Despite the heightened sensitivity of premature infants to auditory stimuli, NICU staff attempt to minimize adverse auditory stimuli and persistent noise that may irritate infants (14). However, the effects of music differ from those of ambient noise. Music has a structured organization and typically lacks rapid fluctuations in amplitude, resulting in responses distinct from those produced by noise (11).
White noise comprises all frequencies audible to humans (From 20 Hz to 20 KHz). These frequencies are transmitted randomly and have equal power (12). White noise has positive effects on infants' feeding and sleep patterns and reduces the duration of crying episodes (9). Because of their shared characteristics, white-noise sounds may resemble those experienced by an infant inside the mother's uterus (13). These sounds are influenced by the mother's heart rate, and postpartum exposure to familiar sounds and rhythms may induce a calming effect in the infant (15,16).
Previous studies have explored the effectiveness of auditory interventions, including white noise and womb sounds, in managing procedural pain and promoting neonatal comfort (17-19). Research by Duken et al., 2024 indicated that white noise could reduce physiological indicators of pain in neonates undergoing suctioning (19). However, findings have varied across studies, and inconsistencies remain regarding optimal parameters (e.g., intensity, duration, and type of sound) and the definitive effect on pain scores specifically during endotracheal suctioning in preterm infants.
Despite the growing body of literature, the effectiveness of white noise specifically during endotracheal suctioning in preterm infants, particularly in diverse cultural contexts such as ours, requires further investigation. Based on their experience caring for premature infants in the NICU, the limited use of pain-reduction techniques during airway suctioning, and the scarcity of research examining the effects of white noise during suctioning on pain and neonatal physiological parameters, the research team decided to investigate this issue.
This study aimed to investigate the effect of white noise during endotracheal suctioning on pain intensity and physiological parameters in preterm neonates admitted to the NICU. It was hypothesized that exposure to white noise would reduce pain and improve physiological responses during the procedure.
Methods
This study was a parallel-group, randomized controlled clinical trial using simple random sampling. The study population comprised premature infants hospitalized in the NICU of Afzalipour Hospital in Kerman. The study was conducted between June, 2023 and January, 2024.
Sample size and sampling
Fifty premature infants who met the inclusion criteria and were admitted to the NICU constituted the study sample. Based on a previous study and Coldak's formula, the required sample size was determined to be 44 with 80% power. Consequently, 50 participants were enrolled to allow for a 10% attrition rate (20). The sample size was calculated using [Specify the formula, e.g., the formula for comparing two independent means] based on parameters from a previous study by Zeraati (2018), which reported an effect size relevant to pain scores, with a target power of 80% and an alpha level of 0.05 (20). Reference (18) describes the methodology and findings of this foundational study. Eligible premature infants were selected randomly and assigned to the intervention or control group using a random-number table.
The inclusion criteria were as follows: preterm infants born between 28 and 36 weeks of gestational age; hospitalization in the NICU for a minimum of three days; a fifth-minute Apgar score of 7 or above; absence of congenital abnormalities, such as heart disease or hydrocephalus; no maternal history of alcohol or drug use; absence of diagnosed hearing disorders; absence of acute conditions, such as sepsis, necrotizing enterocolitis, asphyxia, or acute respiratory problems; infant weight greater than 1500 grams; and confirmation of normal hearing by a physician (20). The exclusion criteria were premature death or discharge before the third day; severe responses to auditory stimuli, including screaming, crying, and movement difficulty; and any notable behavioral or physiological changes, such as a decrease in oxygen saturation below 75 or an increase in heart rate above 200 (20).
Eligible neonates were identified through a review of their medical records according to the inclusion criteria. After the parents had been informed about the study, written informed consent was obtained before enrollment.
Allocation concealment was achieved using sequentially numbered, opaque, sealed envelopes (SNOSE). Each envelope contained a card indicating the group assignment (Intervention or control). The envelopes were prepared by an independent researcher who was not involved in patient recruitment or care and were opened by the bedside nurse only after the infant met the eligibility criteria and immediately before the intervention was initiated.
Demographic information and pain measurements were obtained for both groups before, during, and after the intervention.
Because of the nature of the auditory intervention, blinding the infants, parents, and bedside nurses who performed suctioning was not feasible. However, the outcome assessors who administered the pain scales and monitored physiological parameters were blinded to group allocation (Figure 1).
Intervention
In the intervention group, infants requiring suctioning while in the incubator received womb sounds through headphones connected to an MP3 player. Auditory stimulation began 5 minutes before suctioning and continued for 10 minutes after the procedure. The intervention was conducted during the evening shift because the ward was quieter at that time (10). Before the intervention, an audiologist used an audiometer to set the sound intensity to 45 dB (21). Headphones were placed over the infants' ears to attenuate surrounding disturbances while white noise was played. Each infant was continuously supervised by two individuals, a ward nurse and a research colleague, and all infant behaviors were documented. Suctioning was performed only when clinically necessary to improve respiration; no infant underwent suctioning solely for research purposes. Normal saline was not used during suctioning for any participant. Suction pressure followed the standard protocol and ranged from 80 to 100 mmHg (6). Adherence to the neonatal suctioning protocol was ensured, with careful attention to the procedure and associated nursing care for all infants. The researcher completed the pain measurement scale during and after suctioning (10).
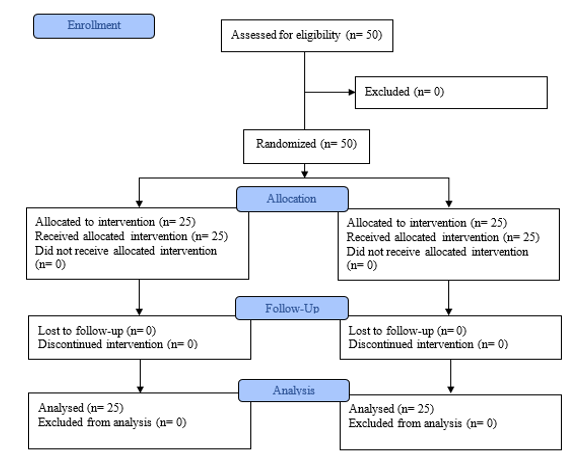 Figure 1. Consort flow diagram |
When immediate clinical needs required urgent suctioning (e.g., severe bradycardia, desaturation below 75%, or significant respiratory distress), the 5-minute pre-intervention auditory-stimulation period was to be omitted, and suctioning was to be performed immediately according to the standard clinical protocol. However, no infant required omission of the 5-minute pre-intervention white-noise exposure because of an emergency clinical condition. Therefore, all randomized participants received the intervention according to the study protocol and were included in the final per-protocol analysis.
Monitoring equipment and timing: Physiological parameters, including heart rate (bpm), respiratory rate (Breaths/Min), and oxygen saturation (SpO2 %), were continuously monitored using a standard neonatal vital-signs monitor. Data were recorded at baseline (Before the intervention), during suctioning, and 10 minutes after the procedure.
Control
The researcher completed the pain-assessment checklist for infants in the control group before, during, and ten minutes after suctioning. Infants in the control group received no music, and suctioning care was provided according to the same protocol. A nurse performed all suctioning procedures during the study. Both study groups were assessed at the same time points.
The primary outcome was the neonate's pain score, assessed using the Neonatal Infant Pain Scale (NIPS), immediately before, during, and 10 minutes after the suctioning procedure.
Secondary outcomes included changes in physiological parameters, such as heart rate (Beats per minute), respiratory rate (Breaths per minute), and oxygen saturation (SpO2 %), which were continuously monitored and recorded at the same time points as the primary outcome assessment (Before, during, and 10 minutes after suctioning).
Measure
Data collection
The data-collection instrument consisted of three sections.
The first section collected maternal demographic data, including age, educational attainment, number of children, mode of delivery, hospitalization history, pregnancy intention, number of previous deliveries, place of residence, and economic status (22).
The second section collected infant demographic data, including age, weight, sex, height, head circumference, first- and fifth-minute Apgar scores, and congenital anomalies. It also collected hospitalization-related information, including the reason for admission, length of stay, and serum and oxygen intake (22).
Neonatal Infant Pain Scale (NIPS)
The NIPS is a widely used multidimensional pain-assessment tool specifically designed for neonates with a gestational age of 28 to 38 weeks. It is a behavioral instrument for measuring pain in both term and preterm infants and comprises six components: five behavioral components (Facial expression, crying, arm movement, leg movement, and state of arousal) and one physiological component (Breathing pattern). Each item is scored as zero or one, except crying, which is scored as zero, one, or two. The total pain score ranges from 0 to 7. The instrument can be used to monitor pain before and after a painful procedure. A score of zero indicates the minimum pain level, whereas a score of seven indicates the maximum pain level. The instrument has demonstrated high validity and reliability (23).
The Neonatal Infant Pain Scale (NIPS) 22 is a validated instrument for assessing procedural pain in neonates. Its reliability and validity have been established in various international settings. Although validation studies of the NIPS in the Iranian neonatal population may be limited, reference 22 used this scale, and the present study adopted it because of its widespread international acceptance and clinical applicability. Outcome assessors received standardized training in NIPS administration to ensure consistent scoring.
Data analysis
Data were analyzed using SPSS software version 23. Descriptive statistics, including the mean, standard deviation, frequency, and percentage, were used to summarize the data. Fisher’s exact test and the Chi-square test were used to compare demographic and qualitative baseline variables between the two groups. Repeated-measures ANOVA with Greenhouse-Geisser correction was the primary statistical method used to evaluate changes in pain scores and physiological parameters over time and to assess the group-by-time interaction. An independent t-test was additionally used to compare mean values between the intervention and control groups at each measurement time point. Effect sizes were reported as partial eta squared (η²). A p-value less than 0.05 was considered statistically significant.
Results
A total of 50 preterm neonates were randomized and allocated equally to the intervention (n = 25) and control (n = 25) groups. No participants were lost to follow-up, discontinued the intervention, or were excluded from the final analysis. Therefore, all randomized participants were included in the final analysis.
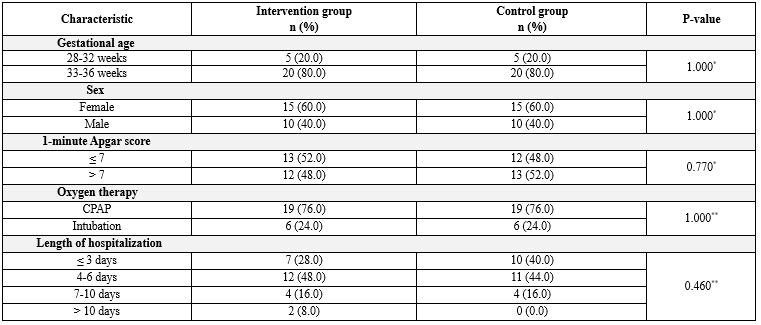
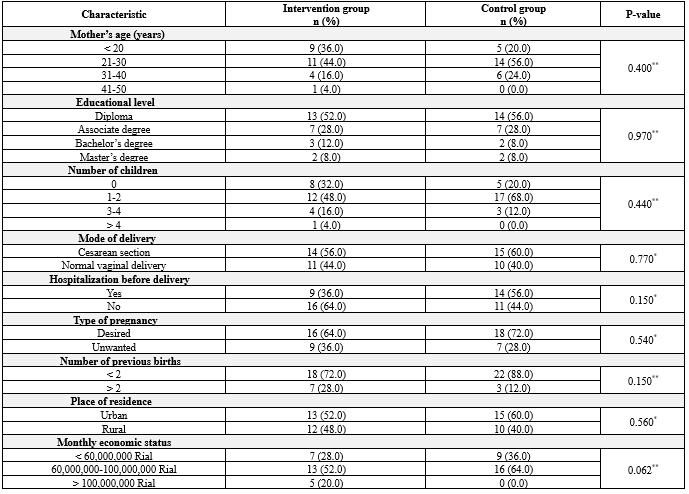
No significant differences were observed between the intervention and control groups in neonatal or maternal demographic variables (P> 0.05) (Table 1 and 2). Repeated-measures ANOVA demonstrated a significant effect of time on pain scores and a significant group-by-time interaction, indicating that pain responses differed between the intervention and control groups across measurement occasions (P<0.001). Infants exposed to white noise had significantly lower pain scores during suctioning than those in the control group. In addition to statistical significance, effect sizes (Partial η²) were calculated to estimate the magnitude of the intervention effect and are reported in the corresponding tables.
Monitoring equipment and timing: Physiological parameters, including heart rate (bpm), respiratory rate (Breaths/Min), and oxygen saturation (SpO2 %), were continuously monitored using a standard neonatal vital-signs monitor. Data were recorded at baseline (Before the intervention), during suctioning, and 10 minutes after the procedure.
Control
The researcher completed the pain-assessment checklist for infants in the control group before, during, and ten minutes after suctioning. Infants in the control group received no music, and suctioning care was provided according to the same protocol. A nurse performed all suctioning procedures during the study. Both study groups were assessed at the same time points.
The primary outcome was the neonate's pain score, assessed using the Neonatal Infant Pain Scale (NIPS), immediately before, during, and 10 minutes after the suctioning procedure.
Secondary outcomes included changes in physiological parameters, such as heart rate (Beats per minute), respiratory rate (Breaths per minute), and oxygen saturation (SpO2 %), which were continuously monitored and recorded at the same time points as the primary outcome assessment (Before, during, and 10 minutes after suctioning).
Measure
Data collection
The data-collection instrument consisted of three sections.
The first section collected maternal demographic data, including age, educational attainment, number of children, mode of delivery, hospitalization history, pregnancy intention, number of previous deliveries, place of residence, and economic status (22).
The second section collected infant demographic data, including age, weight, sex, height, head circumference, first- and fifth-minute Apgar scores, and congenital anomalies. It also collected hospitalization-related information, including the reason for admission, length of stay, and serum and oxygen intake (22).
Neonatal Infant Pain Scale (NIPS)
The NIPS is a widely used multidimensional pain-assessment tool specifically designed for neonates with a gestational age of 28 to 38 weeks. It is a behavioral instrument for measuring pain in both term and preterm infants and comprises six components: five behavioral components (Facial expression, crying, arm movement, leg movement, and state of arousal) and one physiological component (Breathing pattern). Each item is scored as zero or one, except crying, which is scored as zero, one, or two. The total pain score ranges from 0 to 7. The instrument can be used to monitor pain before and after a painful procedure. A score of zero indicates the minimum pain level, whereas a score of seven indicates the maximum pain level. The instrument has demonstrated high validity and reliability (23).
The Neonatal Infant Pain Scale (NIPS) 22 is a validated instrument for assessing procedural pain in neonates. Its reliability and validity have been established in various international settings. Although validation studies of the NIPS in the Iranian neonatal population may be limited, reference 22 used this scale, and the present study adopted it because of its widespread international acceptance and clinical applicability. Outcome assessors received standardized training in NIPS administration to ensure consistent scoring.
Data analysis
Data were analyzed using SPSS software version 23. Descriptive statistics, including the mean, standard deviation, frequency, and percentage, were used to summarize the data. Fisher’s exact test and the Chi-square test were used to compare demographic and qualitative baseline variables between the two groups. Repeated-measures ANOVA with Greenhouse-Geisser correction was the primary statistical method used to evaluate changes in pain scores and physiological parameters over time and to assess the group-by-time interaction. An independent t-test was additionally used to compare mean values between the intervention and control groups at each measurement time point. Effect sizes were reported as partial eta squared (η²). A p-value less than 0.05 was considered statistically significant.
Results
A total of 50 preterm neonates were randomized and allocated equally to the intervention (n = 25) and control (n = 25) groups. No participants were lost to follow-up, discontinued the intervention, or were excluded from the final analysis. Therefore, all randomized participants were included in the final analysis.
No significant differences were observed between the intervention and control groups in neonatal or maternal demographic variables (P> 0.05) (Table 1 and 2). Repeated-measures ANOVA demonstrated a significant effect of time on pain scores and a significant group-by-time interaction, indicating that pain responses differed between the intervention and control groups across measurement occasions (P<0.001). Infants exposed to white noise had significantly lower pain scores during suctioning than those in the control group. In addition to statistical significance, effect sizes (Partial η²) were calculated to estimate the magnitude of the intervention effect and are reported in the corresponding tables.
As shown in Table 3, pain scores changed significantly over time, with significant effects of time, group, and the time × group interaction (P<0.001). Pain intensity increased during the intervention in both groups. After the intervention, pain scores returned to baseline in the intervention group but remained above baseline in the control group.
As shown in Table 4, heart rate changed significantly over time in both groups (P< 0.001). Heart rate increased during the intervention and decreased afterward in both groups. Pairwise comparisons showed significant differences among all measurement time points. In addition, heart rate was significantly lower in the intervention group than in the control group at all time points.
As shown in Table 5, oxygen saturation and respiratory rate changed significantly over time in both groups (P< 0.001). Oxygen saturation was significantly higher in the intervention group during suctioning, and the time × group interaction was significant for both oxygen saturation and respiratory rate, indicating different patterns of change between the groups. In contrast, body temperature remained stable over time, with no significant effects of time, group, or their interaction.
As shown in Table 4, heart rate changed significantly over time in both groups (P< 0.001). Heart rate increased during the intervention and decreased afterward in both groups. Pairwise comparisons showed significant differences among all measurement time points. In addition, heart rate was significantly lower in the intervention group than in the control group at all time points.
As shown in Table 5, oxygen saturation and respiratory rate changed significantly over time in both groups (P< 0.001). Oxygen saturation was significantly higher in the intervention group during suctioning, and the time × group interaction was significant for both oxygen saturation and respiratory rate, indicating different patterns of change between the groups. In contrast, body temperature remained stable over time, with no significant effects of time, group, or their interaction.
|
Table 3. Comparison of pain scores between intervention and control groups across time and results of repeated-measures ANOVA
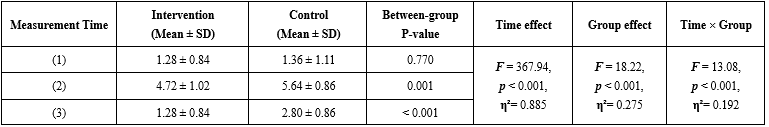 (1) Before intervention, (2) During intervention, (3) After intervention Mean ± Standard Deviation (SD) Between-group comparisons at each time point were performed using the independent-samples t-test. Partial η² values represent effect sizes. Table 4. Comparison of heart rates between intervention and control groups across time and results of repeated-measures ANOVA 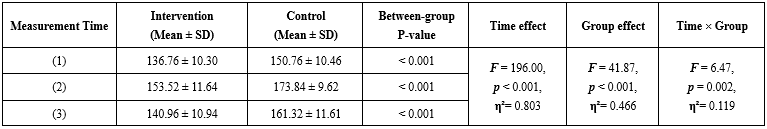 (1) Before intervention, (2) During intervention, (3) After intervention Mean ± Standard Deviation (SD) Between-group comparisons at each time point were performed using the independent-samples t-test. Partial η² values represent effect sizes. Table 5. Comparison of oxygen saturation (SpO₂), respiratory rate, and body temperature between intervention and control groups at different time points (n = 50) 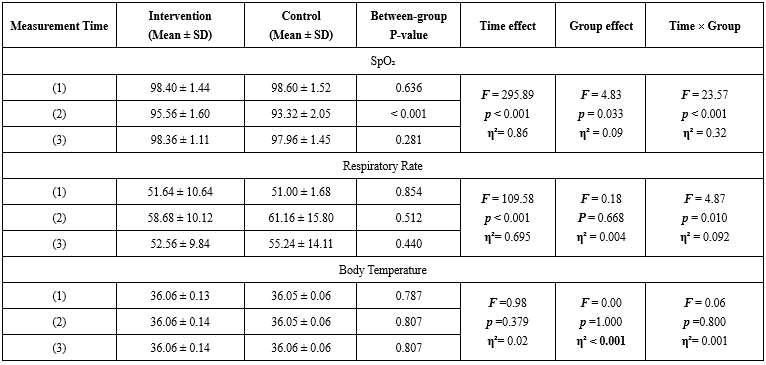 (1) Before intervention, (2) During intervention, (3) After intervention Mean ± Standard Deviation (SD) Between-group comparisons at each time point were performed using the independent-samples t-test. Partial η² values represent effect sizes. |
Discussion
This study investigated the effects of white noise on pain levels and physiological parameters in premature infants during airway suctioning. The findings demonstrated that white noise was effective in alleviating pain during airway suctioning in premature infants.
Consistent with the present findings, Taplak (2021) conducted a study of 80 infants to evaluate the effects of breast-milk odor, white noise, and the fetal position on pain during airway suctioning. The results indicated that both white noise and the fetal position before intratracheal suctioning significantly reduced pain (24). That study evaluated the effect of white noise on pain during tracheostomy suctioning in infants, similar to the present investigation. However, it used the PIPP tool to measure pain, which differed from the instrument used in the present study.
Although routine suctioning is not recommended in the NICU, it may be necessary in emergencies. Studies indicate that suctioning is both unavoidable and uncomfortable (6). Pekygit (2023) studied 90 infants to examine the effects of white noise and the fetal position on pain during heel sampling. Infants who received a combination of white noise and fetal-position interventions experienced significantly less pain than those in the other two groups (25). That study focused on term infants and evaluated the effectiveness of combining two non-pharmacological interventions, namely white noise and the fetal position, to alleviate infant pain. This approach differed from that used in the current study. Further research is needed to evaluate the effectiveness of combined non-pharmacological interventions in this area.
In a study of 66 infants, Ren (2022) found that white noise did not positively affect cortical pain responses, pain scores, or behavioral and physiological parameters in infants experiencing pain (21). This finding contradicts the results of the current study. One possible explanation for this discrepancy is the difference in study populations: the previous study examined term infants, whereas the current study examined preterm infants. Furthermore, the white noise used in the present study differed substantially from that used in the previous study. Specifically, the previous study used music as white noise, whereas the current study used sounds generated from the uterus and heartbeat. Kucukoglu (2016) examined the effect of white noise on vaccination pain in premature infants and found that the intervention group experienced significantly lower pain levels. In that study, an MP3 player was used to emit white noise, whereas in the present study, infants wore headphones set to 45 dB (18). The duration and type of auditory stimulus used to generate white noise also differed considerably from those in the present investigation. Nevertheless, headphones may be more advantageous for evaluating the effect of sound on infants because they provide more comprehensive auditory coverage.
Consistent with the study’s second objective, which was to examine the effect of white noise on physiological parameters in premature infants, the findings showed beneficial effects on heart rate and oxygen saturation during airway suctioning. Similarly, Düken (2023) examined the effects of massage and white noise on physiological indicators in premature infants. Premature infants who received massage and were exposed to white noise in the morning and evening for three consecutive days showed significant differences in peak heart rate, respiratory rate, and oxygen saturation compared with the control group. However, no significant differences were observed between the white-noise and massage groups. In agreement with the present findings, white noise was effective in influencing the physiological parameters of premature infants (19). One difference between the two studies was the duration of the white-noise intervention. The intervention lasted three days in the previous study but only approximately 20 minutes in the current study because of the researcher’s time constraints.
Kim and Hye (2023) examined the effect of white noise on heart-rate responses and oxygen saturation during heel sampling in premature infants. Premature infants in the intervention group had a lower heart rate and higher oxygen saturation than those in the control group (17). Various forms of white noise have been used as non-pharmacological pain-relief interventions to evaluate their effects on physiological parameters. These include music, recitation of the Quran (26), heartbeat sounds (19), the mother’s voice (27), and the mother’s lullaby (10). Liao (2021) examined the effects of maternal voice and white noise on the physiological responses of 103 premature infants admitted to the NICU. Infants were exposed to white noise without their mother’s voice for 20 minutes, three times a day, over four consecutive days. The findings showed a significant increase in oxygen saturation. However, no significant differences in salivary cortisol levels or heart rate were observed among the three groups (27). The intervention in that study was longer than that in the current study, and white noise was more effective than the mother’s voice. In the current study, however, the intervention was administered before, during, and after airway suctioning, a painful procedure.
This study was limited by recruitment from a single treatment-teaching center. Additional limitations included the small sample size and the short intervention period imposed by the student’s time constraints. Further multicenter trials are needed to confirm these findings across a broader range of NICU settings and establish the generalizability of the white-noise intervention.
Conclusion
The findings demonstrated that white noise comprising the mother’s heartbeat and uterine sounds affected infants’ blood oxygen levels, heart rates, and pain levels during airway suctioning. Therefore, nurses should consider using white noise as a non-pharmacological pain-relief intervention. Nurses should be aware of the potential effects of this method and seek to implement it in the ward to alleviate pain in infants, who are highly sensitive to painful stimuli. NICU nurses are encouraged to use auditory stimuli, such as white noise, to help reduce the short- and long-term effects of pain in infants.
Acknowledgement
The authors would like to thank all staff members of the neonatal intensive care unit at Afzalipour Hospital in Kerman for their cooperation.
Funding Sources
None.
Ethical Statement
The study was initiated after approval was obtained from the Ethics Committee of Kerman University of Medical Sciences (IR.KMU.REC.1402.147) and registration of the clinical trial (IRCT20221213056807N1). Written informed consent was obtained from the parents of all participating neonates after they had received adequate information regarding the study objectives, procedures, potential risks, and expected benefits. The study was conducted in accordance with the ethical principles of the Declaration of Helsinki. Participation was entirely voluntary, and parents were informed of their right to decline participation or withdraw their neonates from the study at any time without any consequences for their care or benefits. Participant confidentiality was strictly maintained through data coding and anonymization. All study data were stored securely and were accessible only to authorized research personnel.
Conflicts of Interest
The funding organization(s) played no role in the study design; data collection, analysis, or interpretation; or preparation of the report.
Author Contributions
This manuscript resulted from the collaboration of all authors. SA and ZKH designed the study and prepared the study proposal, and NS and SA conducted data collection and analysis. MN and NS analyzed the data, while RM and MN wrote the final draft of the manuscript and prepared the tables. RM submitted the manuscript to the journal. The author(s) read and approved the final manuscript.
Data Availability Statement
The datasets generated and analyzed during the current study are available from the corresponding author upon reasonable request.
Use of Artificial Intelligence
AI was used only for English-language editing, translation assistance, and manuscript proofreading. No AI tools were used for data analysis, interpretation of findings, or generation of scientific conclusions.
Type of study: Original Article |
Subject:
Nursing
References
1. Issa SS, Madwah K, Al Mosawi HS. Evaluation of nurse's knowledge in management Of premature baby in neonatal units. American Journal of Nursing Research. 2018;6(5):291-5. [View at Publisher] [DOI] [Google Scholar]
2. Carvalho SS, de Almeida Soares J, Pinheiro JA, dos Santos Queiroz M. Perception of the nursing team about pain evaluation in premature newborns. Rev Enferm Atenção Saúde. 2021;10(2):e202117. [View at Publisher] [Google Scholar]
3. amiri doomari S, Shahrbabaki RM, Nematollahi M, Bagherian B. The effect of educational- supportive program on the anxiety of mothers of infants admitted to the neonatal intensive care unit (NICU). Journal of Neonatal Nursing. 2025;31(2):101591. [View at Publisher] [DOI] [Google Scholar]
4. Oliveira NRGd, Formiga CKMR, Ramos BA, Noleto RdS, Moreira NNdS, Amaral WNdJB. Reliability and internal consistency in the assessment of neonatal pain in preterm infants during tracheal aspiration: prospective study. BrJP. 2023;5(4):341-6. [View at Publisher] [DOI] [Google Scholar]
5. Bellieni CV. Pain in the Fetus and the Preterm Baby. Meanings of Pain: Volume 3: Vulnerable or Special Groups of People: Springer; 2022. p. 17-32. [View at Publisher] [DOI] [Google Scholar]
6. Niaraki SS, Pouraboli B, Fakhr AS, Mirlashari J, Ranjbar H. The Effect of Endotracheal Suctioning Using the Four-handed Care on Physiological Criteria and Behavioral Responses of the Preterm Infants: Randomized Crossover Clinical Trial. J Caring Sci. 2022;11(1):21-7. [View at Publisher] [DOI] [PMID] [Google Scholar]
7. Shykhveisi F, Jafarian Amiri R, Zabihi A, Haghshenas Mojaveri MH, Arzani A, Chehrazi M, et al. Effect of eye shield and ear muffs on pain intensity during venous blood sampling in premature infants: a clinical trial study. BMC Pediatr. 2023;23(1):161. [View at Publisher] [DOI] [PMID] [Google Scholar]
8. Smith HA, Besunder JB, Betters KA, Johnson PN, Srinivasan V, Stormorken A, et al. 2022 Society of Critical Care Medicine clinical practice guidelines on prevention and management of pain, agitation, neuromuscular blockade, and delirium in critically ill pediatric patients with consideration of the ICU environment and early mobility. Pediatr Crit Care Med. 2022;23(2):e74-e110. [View at Publisher] [DOI] [PMID] [Google Scholar]
9. Kahraman A, Gümüş M, Akar M, Sipahi M, Yılmaz HB, Başbakkal ZJI. The effects of auditory interventions on pain and comfort in premature newborns in the neonatal intensive care unit; a randomised controlled trial. Intensive Crit Care Nurs. 2020;61:102904. [View at Publisher] [DOI] [PMID] [Google Scholar]
10. Pouraboli B, Hosseini F, Rayyani M, Dehghan MJi-MsJoN. The Effect of Recorded Mothers' Lullaby on the Heart Rate of Preterm Neonates Following Endotracheal Suctioning: A Cross-Over Clinical Trial. 2018;8(2):14-22. [View at Publisher] [DOI] [Google Scholar]
11. Smith AR. The conceptualization of a theoretical framework for a music intervention to improve auditory development in very preterm infants: University of Kansas; 2019. [View at Publisher] [Google Scholar]
12. Cetinkaya S, Yavas Celik M, Ozdemir S. Effect of white noise on alleviating the pain of new-born during invasive procedures. J Matern Fetal Neonatal Med. 2022;35(8):1426-32. [View at Publisher] [DOI] [PMID] [Google Scholar]
13. Steiner-Brett ACJTAiP. The use of music therapy to address psychosocial needs of informal caregivers: An integrative review. Arts Psychother. 2023;84:102036. [View at Publisher] [DOI] [Google Scholar]
14. Efendi D, Tane R. The effects of music therapy on vital signs, feeding, and sleep in premature infants. NLJ. 2019;4(1):31-6. [View at Publisher] [DOI] [Google Scholar]
15. Barcellos AA, Mathiolli C, Lagos MTG, Matos GM, Zani AV. Effects of music therapy on the physiological responses of preterm newborns on non-invasive ventilation: a quasi-experimental study/Efeitos da musicoterapia nas respostas fisiologicas dos recem-nascidos pre-termos em ventilacao nao invasiva: estudo quase-experimental/Efectos de la musicoterapia sobre las respuestas fisiologicas de los recien nacidos prematuros con ventilacion no invasiva: estudio cuasiexperimental. Online Braz J Nurs. 2021;20(1):e20216487. [View at Publisher] [DOI] [Google Scholar]
16. Magor NRE, Ads SEM, Elhalafawy SEH. Effectiveness of nesting positioning and Yakson touch on physiological, behavioral state and pain caused by blood sampling procedures in preterm neonates. JNN. 2024;30(5):502-8. [View at Publisher] [DOI] [Google Scholar]
17. Kim MH, Song J-E, Ahn J-A, You M-A. Effect of White Noise on Pain Response, Heart Rate, and Oxygen Saturation During Heel Puncture in Premature Infants: A Randomized Controlled Trial. J Perinat Neonatal Nurs. 2024;38(3):297-305. [View at Publisher] [DOI] [PMID] [Google Scholar]
18. Kucukoglu S, Aytekin A, Celebioglu A, Celebi A, Caner I, Maden R. Effect of white noise in relieving vaccination pain in premature infants. Pain Manag Nurs. 2016;17(6):392-400. [View at Publisher] [DOI] [PMID] [Google Scholar]
19. Düken ME, Yayan EH, Arslan Z. The effects of massage and white noise on physiological parameters of preterm infants: A randomized controlled research.J Neonatal Nurs. 2024;30(4):360-7. [View at Publisher] [DOI] [Google Scholar]
20. Zeraati H, Nasimi F, Rezaeian A, Shahinfar J, Zade MG. Effect of multi-sensory stimulation on neuromuscular development of premature infants: a randomized clinical trial. Iran J Child Neurol. 2018;12(3):32-9. [View at Publisher] [PMID] [Google Scholar]
21. Ren X, Li L, Lin S, Zhong C, Wang B. Effects of white noise on procedural pain-related cortical response and pain score in neonates: A randomized controlled trial. Int J Nurs Sci. 2022;9(3):269-77. [View at Publisher] [DOI] [PMID] [Google Scholar]
22. Namjoo R, Mehdipour-Rabori R, Bagherian B, Nematollahi M. Comparing the effectiveness of mother's live lullaby and recorded lullaby on physiological responses and sleep of preterm infants: a clinical trial study. J Complement Integr Med. 2021;19(1):121-9. [View at Publisher] [DOI] [PMID] [Google Scholar]
23. Huang X-Z, Li L, Zhou J, He F, Zhong CX, Wang B. Evaluation of three pain assessment scales used for ventilated neonates. J Clin Nurs. 2018;27(19- 20):3522-9. [View at Publisher] [DOI] [PMID] [Google Scholar]
24. Taplak AŞ, Bayat M. Comparison the effect of breast milk smell, white noise and facilitated tucking applied to Turkish preterm infants during endotracheal suctioning on pain and physiological parameters. J Pediatr Nurs. 2021;56:e19-e26. [View at Publisher] [DOI] [PMID] [Google Scholar]
25. Pekyigit A, AÇIKGÖZ A. Effects of White Noise and Facilitated Tucking During Heel Stick Sampling on the Pain Response of Healthy Term Newborns: A Randomized Controlled Study. JPR. 2023;10(1):43-54. [View at Publisher] [DOI] [Google Scholar]
26. Aisyah PS, Sofiyah Y, Pangestuty E. The effect of the sound of Holy Quran on pain level of neonates during invasive procedure. KnE Life Sciences. 2019;4(13):789–97. [View at Publisher] [DOI] [Google Scholar]
27. Liao J, Liu G, Xie N, Wang S, Wu T, Lin Y, et al. Mothers' voices and white noise on premature infants' physiological reactions in a neonatal intensive care unit: A multi-arm randomized controlled trial. Int J Nurs Stud. 2021;119:103934. [View at Publisher] [DOI] [PMID] [Google Scholar]
Send email to the article author
| Rights and permissions | |
 |
This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License. |
