
Volume 23, Issue 1 (3-2026)
J Res Dev Nurs Midw 2026, 23(1): 5-10 |
Back to browse issues page


Download citation:
BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:


BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:
Medina-Fernández I, Casas-Patiño D, Rodríguez-Torres A, Medina-Fernández J, Valdés-García K P, Carrillo-Cervantes A L. Influence of attitudes toward death, vulnerability to abuse, and family functioning on suicide Riskin Mexican older adults. J Res Dev Nurs Midw 2026; 23 (1) :5-10
URL: http://nmj.goums.ac.ir/article-1-2292-en.html
URL: http://nmj.goums.ac.ir/article-1-2292-en.html
Isaí Medina-Fernández1 

 , Donovan Casas-Patiño2 , Alejandra Rodríguez-Torres3 , Josué Medina-Fernández4 , Karla Patricia Valdés-García1 , Ana Laura Carrillo-Cervantes1
1- Universidad Autónoma de Coahuila, Saltillo, Coahuila, México
2- Centro Universitario UAEM Amecameca, Universidad Autónoma del Estado de México, Amecameca, Estado de México, México ,capo730211@yahoo.es
3- Centro Universitario UAEM Amecameca, Universidad Autónoma del Estado de México, Amecameca, Estado de México, México
4- Universidad Autónoma del Estado de Quintana Roo, Chetumal, Quintana Roo, México
2- Centro Universitario UAEM Amecameca, Universidad Autónoma del Estado de México, Amecameca, Estado de México, México ,
3- Centro Universitario UAEM Amecameca, Universidad Autónoma del Estado de México, Amecameca, Estado de México, México
4- Universidad Autónoma del Estado de Quintana Roo, Chetumal, Quintana Roo, México
Full-Text [PDF 431 kb]
(1096 Downloads)
| Abstract (HTML) (3830 Views)
Discussion
The objective of this study was to determine the explanatory power of the attitudes towards death, vulnerability to abuse, and family functionality on suicide risk in older adults. The results confirm that suicidal behavior in old age is a multidimensional phenomenon, in which individual, relational, and contextual factors converge, with family functionality being the element with the greatest explanatory weight.
Descriptively, a notable proportion of older adults presented a risk of suicide, even though the majority were married and without chronic diseases. This coincides with previous studies indicating that suicidal risk in old age does not depend exclusively on physical illness, but also on less visible psychosocial conditions (6,22). This finding reinforces the need to analyze suicide in older adults beyond the traditional biomedical model.
Regarding attitude towards death, the results indicate an ambivalent posture characterized by the coexistence of acceptance and rejection. This pattern has been documented in previous research, which shows that, although older people may show acceptance of the life cycle and death as a natural event, fears associated with suffering, dependence, and loss of control persist (11,23). The absence of a significant correlation between the attitudes towards death and the risk of suicide suggests that this variable, by itself, does not constitute a direct risk factor, but rather its influence could be mediated by other elements, such as family functionality or the presence of abuse.
Regarding vulnerability to abuse, a positive and significant correlation was identified with suicide risk, which confirming its relevance as a psychosocial risk factor. International research has shown that abuse, even in its less visible forms such as emotional neglect or coercion, increases suicidal ideation by generating feelings of helplessness, humiliation, and hopelessness in older adults (24). The observed correlation supports the usefulness of the VASS scale as an early detection instrument, as it facilitates the identification of risk conditions before abuse becomes explicit (25).
A central finding of the study was the inverse relationship between family functionality and suicide risk, as well as its negative association with vulnerability to abuse. These results align with the literature, which positions the family as a fundamental axis in protecting mental health in old age. A functional family fosters communication, emotional support, and effective conflict resolution, factors that decrease the chance of self-destructive behaviors (16,26).
The correlational analysis also showed that the older you are, the greater the risk of suicide and lower family functionality, which coincides with research that indicates that advanced aging can imply a progressive reduction in support networks, greater dependency, and increased perception of burden, especially in fragile family contexts (3). This finding reinforces the importance of considering age not only as a chronological variable but as a marker of accumulated social vulnerability.
The multiple linear regression model showed that the variables analyzed explained 17.4% of the variance in suicide risk. This figure aligns with previous research in elderly populations where psychosocial factors tend to have moderate yet meaningful explanatory power. Within the model, family functioning was the only significant predictor, highlighting its important protective role against suicide risk. The lack of significance of attitude toward death and vulnerability to abuse in the final model were not statistically significant. Their effects might be influenced or moderated by family functioning, indicating that family dynamics play a key regulatory role.
From the perspective of collective health, these results confirm that the risk of suicide in older adults cannot be understood as an isolated individual phenomenon, but as the result of social, family, and symbolic processes that accumulate throughout the life course. Family functionality acts as a structural factor affecting both abuse exposure and how death and aging are perceived and reinterpreted. In this sense, the findings provide evidence for the design of prevention strategies that strengthen family and community networks and for the early detection of situations of social vulnerability (27).
A study argues that culture influences perceptions of death and suicide through shared beliefs, values, and meanings that shape how individuals interpret suffering, hopelessness, and the meaning of life; therefore, culture may act as a protective factor against suicide risk (28). Paphitis and cols indicate that domestic abuse is an important risk factor for suicide. Similarly, the present study found a relationship between abuse and suicide risk; however, it was not identified as a predictive factor, although it was associated with an increased risk (29).
Family functioning was identified as a predictive factor in this study, consistent with evidence indicating that, in Latino populations, family may constitute a risk factor for suicidal behavior when dysfunctional family dynamics, abuse, substance use, or limited emotional support are present, thereby increasing psychological vulnerability and suicide risk (30).
The present study has limitations that should be considered when interpreting the results. Its cross-sectional design does not allow establishing causal relationships between variables and limits the analysis to identifying associations. The non-probabilistic convenience sampling restricts the generalizability of the findings to the older adult population as a whole, as the sample was obtained exclusively in the city of Saltillo, Coahuila. Additionally, the use of self-report instruments may have introduced social desirability bias, particularly in sensitive variables such as suicide risk and vulnerability to abuse. Finally, the moderate explanatory capacity of the model suggests the influence of other factors not considered in this study.
It is recommended to systematically incorporate the assessment of family functioning and vulnerability to abuse into primary and community care for older adults as part of suicide prevention strategies. Strengthening the training of healthcare personnel in the early detection of psychosocial risk factors with a collective health approach is necessary. Likewise, future research is encouraged to use longitudinal designs and probabilistic sampling, include additional variables, and consider qualitative methodologies that allow for a deeper exploration of the subjective experiences of aging and suicide risk.
Conclusion
The findings of this study confirm that suicide risk in older adults is a multifactorial phenomenon influenced by psychosocial and family-related variables. Among the factors analyzed, family functionality emerged as the only significant predictor and the variable with the greatest explanatory weight, demonstrating an inverse relationship with suicide risk and vulnerability to abuse. While vulnerability to abuse correlated positively with suicide risk, it was not a significant predictor in the multivariate model. Likewise, attitude toward death presented an ambivalent pattern and did not demonstrate predictive capacity. Overall, the explanatory model accounted for 17.4% of the variance in suicide risk, highlighting the relevance of relational and contextual factors in late adulthood.
From an applied perspective, these results underscore the importance of strengthening family environments as a key strategy for suicide prevention in older adults. Interventions should prioritize early detection of family dysfunction and vulnerability to abuse, incorporating screening tools into primary health care and community programs. Public health policies should promote family-based and community-based support networks, foster social inclusion, and enhance multidisciplinary strategies aimed at protecting the mental health of older adults. Effectively addressing suicide risk from a collective health perspective necessitates integrating psychosocial assessment into routine geriatric care and strengthening protective family dynamics.
Future research should explore additional psychosocial, cultural, and structural variables that may increase the explanatory capacity of suicide risk models in older populations. Longitudinal studies are recommended to better understand causal relationships and temporal dynamics among family functioning, abuse vulnerability, and suicide risk. Furthermore, qualitative approaches could provide deeper insight into the subjective experiences of older adults, contributing to the development of more culturally sensitive and context-specific prevention strategies.
Acknowledgement
The valuable participation of the older adults who took part in the study is acknowledged, as well as the collaboration of the research team in data collection.
Funding Sources
Not applicable
Ethical Statement
This study complied with the provisions of the General Health Law on Health Research in Mexico and the Official Mexican Standard (31) NOM-012-SSA3-2012 for research involving human participants. Ethical approval was obtained from the Ethics Committee of the Contemporary University of the Americas. The official ethics approval reference number assigned by the Ethics Committee is: EAD12021-030.
Written informed consent was obtained from all participants prior to data collection. Participants were informed about the study objectives, the voluntary nature of participation, confidentiality measures, and their right to withdraw at any time. Due to the sensitive nature of the study, data collection was conducted by trained personnel capable of identifying emotional distress; assessments were paused or discontinued according to participants’ preferences. When suicide risk was identified, a referral protocol was activated to provide immediate guidance and referral to local mental health services for professional evaluation and follow-up. All collected information was anonymized and handled confidentially.
Conflicts of Interest
The Authors declares that there is no conflict of interest.
Author Contributions
IAMF and DCP conceptualized and designed the study. ART contributed to data collection and preliminary analysis. JAMF performed statistical analyses and contributed to the interpretation of results. KPVG provided critical insights and supervised the research methodology. IAMF and ALCC provided overall project supervision, drafted the manuscript, and coordinated revisions. All authors reviewed, edited, and approved the final version of the manuscript.
Data Availability Statement
The datasets generated and/or analyzed during the present study are not publicly available due to confidentiality and ethical restrictions.
Use of Artificial Intelligence
AI-assisted tools were used to support language editing; these tools were not involved in data analysis, the writing of scientific content, the interpretation of results, or scientific decision-making.
Full-Text: (478 Views)
Introduction
Aging is not merely a biological process marked by accumulated cellular damage, physical decline, and increased disease risk; it also involves profound psychosocial transitions (1).
The psychological dimension is fundamental to human well-being. Emotions and feelings play a crucial role in how individuals perceive themselves and their reality. Socially, an older adult navigates two intersecting realms: microsocial processes, which encompass personal interactions, and macrosocial aspects that frame their experiences and influence their behaviors (2).
As these biological and social shifts become more pronounced with age, older adults frequently face new personal, health, and community challenges. This vulnerability underscores why biopsychosocial and family elements are of utmost importance for successful adaptation during this stage of life (3).
When the inevitable transformations of old age make adaptation difficult, they can sometimes result in a predisposition to self-destructive behaviors (4).
One of the most severe self-destructive behaviors is suicide, driven by a desire to end profound physical or psychological pain (5). Deaths by suicide constitute a global phenomenon with a complex approach, considered a public health problem. According to available evidence, multiple variables influence its incidence, with varying importance across life cycle stages (6).
While suicide rates generally decrease with age for women, the opposite is true for men. Men over the age of 65 die by suicide seven times more often than women in the same age range (7). Moreover, older adults often use highly lethal and accessible methods, such as hanging, jumping from heights, firearms, poisoning, and carbon monoxide exposure (5).
According to recent data from the World Health Organization (WHO), more than 800,000 people die by suicide each year worldwide. The suicide rate among men is approximately double that of women, with 12.6 and 5.4 cases per 100,000 inhabitants, respectively (8). Mexico is among the 10 countries with the highest suicide rates, with an estimated rate of 6.5 per 100,000 people. The Instituto Nacional de Estadística y Geografía (INEGI) reported 8,351 deaths due to self-inflicted injuries in 2021.
Coahuila, Mexico, reports an even higher suicide rate of 9.7 per 100,000 inhabitants (9).
The above may be related to various factors; however, for this study, the variables of attitude toward death, vulnerability to abuse, and family functionality will be considered as factors related to the risk of suicide in older adults. For the purpose of this study, attitude toward death, vulnerability to abuse, and family functionality are considered as key factors related to suicide risk in older adults. Although death is a universal and irreversible biological fact, older people often experience fear of death, produced by the unpredictability of the unknown (10).
An individual’s attitude towards death is shaped by their emotional response to the idea of their own mortality. Older adults typically present one of four attitudes: indifference, where death is minimized; fear, presenting as anxiety before the dying process; rest, seen as liberation from suffering; and serenity, reflecting a satisfied acceptance of life. These attitudes profoundly affect their decisions and beliefs about end-of-life issues (11).
Consequently, suicide risk is closely related to these attitudes, as certain perspectives can trigger self-destructive actions. These behaviors can be executed consciously or involuntarily, generating severe psychological, emotional, and physical damage (12).
On the other hand, elder abuse is defined as one or more repeated acts that cause harm or suffering to an elderly person, or the failure to take appropriate measures to prevent further harm; This abuse can be physical, emotional, sexual, economic, or due to neglect (12). Older adults are more vulnerable to such mistreatment due to compounding medical conditions, psychological struggles like loneliness and fear of death, and cognitive decline (13).
This vulnerability is exacerbated when they depend (Economically, emotionally, or physically) on their abusers. Each form of elder abuse represents a direct risk factor for suicide. Indeed, a history of abuse is frequently observed among older adults who have attempted or died by suicide (14).
Another factor to study is family functioning; the importance of these variable stems from the fact that the family environment is a significant factor in its members' physical and emotional health (14). Family functionality is the set of interpersonal relationships that allows the satisfaction of each member, prevents the emergence of risk behaviors, and, at the same time, facilitates the comprehensive development of the family group. A family is considered functional when it allows the harmonious passage through each stage of the life cycle, including old age (15). Thus, family functionality is decisive for the presence or absence of risk behaviors, since it can generate behaviors that are harmful to the person, such as the risk of suicide (16).
From collective health, this study seeks to contribute to the prevention of suicide in older adults by strengthening the early detection of risk factors and facilitating the implementation of multidisciplinary intervention strategies that raise awareness in society about aging and social inclusion in order to reduce the vulnerability of this population. This knowledge will be key to developing public policies and actions that promote dignified and healthy aging.
Having said the above, the objective is to determine the explanatory capacity of the attitude towards death, vulnerability to abuse, and family functionality on the risk of suicide in older adults.
Methods
An analytical cross-sectional design was utilized he study (17) aimed to evaluate suicide risk based on three independent variables (Attitude towards death, vulnerability to abuse, and family functionality) using a multiple linear regression analysis. The study population comprised adults aged 60 years and older residing in the state of Coahuila, Mexico, in 2025.
A priori power analysis using G*Power 3.1 for multiple linear regression with four predictors assuming α = 0.05, power = 0.90, and a conservative small-to-medium effect size (f² = 0.15) yielded a minimum required sample of 139 participants. To ensure statistical robustness and account for potential missing data, a target sample size of 197 was established; ultimately, 260 older adults were included in the study.
However, during data collection, more eligible older adults were available and willing to participate than initially anticipated. Given the observational nature of the research and to improve estimate precision and strengthen statistical power, all eligible participants were included, resulting in a final sample of 260 individuals. This larger sample size reduces the risk of Type II error and enhances the robustness of the analyses.
During the data collection period, a total of 260 older adults were approached, of whom 280 agreed to participate in the study, representing an approximate response rate of 92.9%. Reasons for non-participation included lack of time, disinterest, or failure to meet inclusion criteria.
A non-probabilistic convenience sampling method was selected based on feasibility and accessibility considerations. Given the study’s observational nature, this approach efficiently facilitated the recruitment of available and willing older adults.
Inclusion criteria comprised adults aged 60 years or older without cognitive impairment (As determined by the Pfeiffer scale), and providing written informed consent. Exclusion criteria encompassed a previous suicide attempt or severe medical conditions limiting active participation (e.g., hospitalization or palliative care). Elimination criteria included study withdrawal or incomplete assessment instruments.
Instruments
The order of instrument administration was standardized to minimize participant distress, progressing from less sensitive topics (Sociodemographic data, family functionality and vulnerability to abuse) to more sensitive assessments (Attitudes toward death and suicide risk).
Sociodemographic questionnaire
A custom form designed by the authors to collect basic information, including gender, marital status, education level, and history of chronic diseases.
Suicide risk
Assessed using the Plutchik Suicide Risk Scale, a self-report instrument designed to differentiate between individuals with and without suicide risk. The scale consists of 15 items with a dichotomous response format (Yes/No). Each affirmative response scores one point; higher total scores indicate greater suicide risk, with a cut-off point established at 666. The instrument has been validated in Spanish populations, demonstrating adequate psychometric properties, including a Cronbach’s alpha of 0.89 and sensitivity and specificity values of 88%. (18).
Attitude towards death
Assessed using the Revised Profile of Attitudes toward Death (PAM-R), a multidimensional self-report scale consisting of 32 items. The PAM-R comprises four factorially derived dimensions: 1) Fear of death, 2) Approach acceptance, 3) Escape acceptance, and 4) Neutral acceptance. Responses are recorded on a Likert-type scale ranging from totally disagree to totally agree. It demonstrated a Cronbach’s alpha coefficient of 0.89 (19).
Vulnerability to abuse
Assessed using the Vulnerability to Abuse Screening Scale (VASS). The scale consists of 12 dichotomous items (Yes/No) distributed across four domains: vulnerability, dependence, dejection, and coercion. Affirmative responses are scored as one point. Higher total scores indicate greater vulnerability to abuse; a score below 6 suggests vulnerability to abuse. It demonstrated a Cronbach’s alpha coefficient of 0.77 (20).
Family functionality
Assessed with the Family APGAR (Gómez & Ponce, 2010), a 5-item scale evaluating adaptation, partnership, growth, affection, and resolution. Items are scored from 0 to 2, yielding a total score between 0 and 10. It has a reported Cronbach’s alpha of 0.84 (21).
Data collection procedure
Before starting data collection, a schedule of places to visit was compiled, including squares and public areas in the city of Saltillo, Coahuila. Older adults who met the inclusion criteria were identified, and informed consent was obtained from those who agreed to participate. Subsequently, the following instruments were administered: the sociodemographic data card, suicide risk assessment, attitude toward death scale, vulnerability to abuse scale, and finally, the family functionality assessment.
Statistical analysis
Quantitative analyses were performed using SPSS version 25. Categorical and ordinal variables were described using frequencies and percentages, while continuous variables were summarized with means, medians, and standard deviations. The Kolmogorov–Smirnov test indicated that the continuous data did not follow a normal distribution; therefore, Spearman’s rank correlation coefficient was utilized for bivariate analyses.
To address the primary objective, a multiple linear regression model was fitted to estimate the explained variance (R2) and identify the predictive contribution of each independent variable toward suicide risk. This model provides standardized beta coefficients to indicate the direction and strength of associations, thereby clarifying the impact of the investigated psychosocial factors.
Results
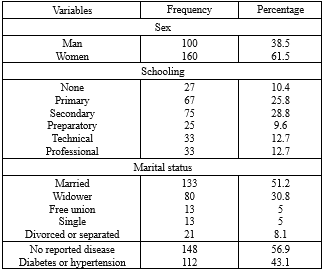
The sample consisted of 260 older adults, whose ages ranged from 60 to 89 (69.25±6.80 years). The majority were women, possessed a secondary education, were married, and reported no chronic diseases (Table 1).
As shown in Table 2, risk of suicide was present in 13.8 (n=36) of the participants. Furthermore, vulnerability to abuse had a prevalence of 10.0% (n=26). Regarding family dynamics, moderate to severe dysfunctionality was reported by 33.9% (n=88) of the sample. Finally, attitudes towards death were generally ambivalent (i.e., demonstrating both acceptance and rejection).
As presented in Table 3, there was a significant positive correlation between age and suicide risk (r = 0.194, p = 0.002). Suicide risk also showed a significant positive correlation with vulnerability to abuse (r = 0.221, p < 0.001) and a significant negative correlation with family functionality (r = -0.380, p < 0.001), the latter being the strongest association in the model. Additionally, higher family functionality was significantly correlated with a less positive attitude toward death (r = -0.135, p = 0.019) and lower vulnerability to abuse (r = -0.282, p < 0.001).
The multiple linear regression model was statistically significant (F = 13.457, p < 0.001) and explained 17.4% of the variance in suicide risk (adjusted R² = 0.174). Among all predictors, family functionality (β = -0.350, p < 0.001) was the strongest and only significant independent predictor, accounting for the largest unique contribution to the model. (Table 4).
Aging is not merely a biological process marked by accumulated cellular damage, physical decline, and increased disease risk; it also involves profound psychosocial transitions (1).
The psychological dimension is fundamental to human well-being. Emotions and feelings play a crucial role in how individuals perceive themselves and their reality. Socially, an older adult navigates two intersecting realms: microsocial processes, which encompass personal interactions, and macrosocial aspects that frame their experiences and influence their behaviors (2).
As these biological and social shifts become more pronounced with age, older adults frequently face new personal, health, and community challenges. This vulnerability underscores why biopsychosocial and family elements are of utmost importance for successful adaptation during this stage of life (3).
When the inevitable transformations of old age make adaptation difficult, they can sometimes result in a predisposition to self-destructive behaviors (4).
One of the most severe self-destructive behaviors is suicide, driven by a desire to end profound physical or psychological pain (5). Deaths by suicide constitute a global phenomenon with a complex approach, considered a public health problem. According to available evidence, multiple variables influence its incidence, with varying importance across life cycle stages (6).
While suicide rates generally decrease with age for women, the opposite is true for men. Men over the age of 65 die by suicide seven times more often than women in the same age range (7). Moreover, older adults often use highly lethal and accessible methods, such as hanging, jumping from heights, firearms, poisoning, and carbon monoxide exposure (5).
According to recent data from the World Health Organization (WHO), more than 800,000 people die by suicide each year worldwide. The suicide rate among men is approximately double that of women, with 12.6 and 5.4 cases per 100,000 inhabitants, respectively (8). Mexico is among the 10 countries with the highest suicide rates, with an estimated rate of 6.5 per 100,000 people. The Instituto Nacional de Estadística y Geografía (INEGI) reported 8,351 deaths due to self-inflicted injuries in 2021.
Coahuila, Mexico, reports an even higher suicide rate of 9.7 per 100,000 inhabitants (9).
The above may be related to various factors; however, for this study, the variables of attitude toward death, vulnerability to abuse, and family functionality will be considered as factors related to the risk of suicide in older adults. For the purpose of this study, attitude toward death, vulnerability to abuse, and family functionality are considered as key factors related to suicide risk in older adults. Although death is a universal and irreversible biological fact, older people often experience fear of death, produced by the unpredictability of the unknown (10).
An individual’s attitude towards death is shaped by their emotional response to the idea of their own mortality. Older adults typically present one of four attitudes: indifference, where death is minimized; fear, presenting as anxiety before the dying process; rest, seen as liberation from suffering; and serenity, reflecting a satisfied acceptance of life. These attitudes profoundly affect their decisions and beliefs about end-of-life issues (11).
Consequently, suicide risk is closely related to these attitudes, as certain perspectives can trigger self-destructive actions. These behaviors can be executed consciously or involuntarily, generating severe psychological, emotional, and physical damage (12).
On the other hand, elder abuse is defined as one or more repeated acts that cause harm or suffering to an elderly person, or the failure to take appropriate measures to prevent further harm; This abuse can be physical, emotional, sexual, economic, or due to neglect (12). Older adults are more vulnerable to such mistreatment due to compounding medical conditions, psychological struggles like loneliness and fear of death, and cognitive decline (13).
This vulnerability is exacerbated when they depend (Economically, emotionally, or physically) on their abusers. Each form of elder abuse represents a direct risk factor for suicide. Indeed, a history of abuse is frequently observed among older adults who have attempted or died by suicide (14).
Another factor to study is family functioning; the importance of these variable stems from the fact that the family environment is a significant factor in its members' physical and emotional health (14). Family functionality is the set of interpersonal relationships that allows the satisfaction of each member, prevents the emergence of risk behaviors, and, at the same time, facilitates the comprehensive development of the family group. A family is considered functional when it allows the harmonious passage through each stage of the life cycle, including old age (15). Thus, family functionality is decisive for the presence or absence of risk behaviors, since it can generate behaviors that are harmful to the person, such as the risk of suicide (16).
From collective health, this study seeks to contribute to the prevention of suicide in older adults by strengthening the early detection of risk factors and facilitating the implementation of multidisciplinary intervention strategies that raise awareness in society about aging and social inclusion in order to reduce the vulnerability of this population. This knowledge will be key to developing public policies and actions that promote dignified and healthy aging.
Having said the above, the objective is to determine the explanatory capacity of the attitude towards death, vulnerability to abuse, and family functionality on the risk of suicide in older adults.
Methods
An analytical cross-sectional design was utilized he study (17) aimed to evaluate suicide risk based on three independent variables (Attitude towards death, vulnerability to abuse, and family functionality) using a multiple linear regression analysis. The study population comprised adults aged 60 years and older residing in the state of Coahuila, Mexico, in 2025.
A priori power analysis using G*Power 3.1 for multiple linear regression with four predictors assuming α = 0.05, power = 0.90, and a conservative small-to-medium effect size (f² = 0.15) yielded a minimum required sample of 139 participants. To ensure statistical robustness and account for potential missing data, a target sample size of 197 was established; ultimately, 260 older adults were included in the study.
However, during data collection, more eligible older adults were available and willing to participate than initially anticipated. Given the observational nature of the research and to improve estimate precision and strengthen statistical power, all eligible participants were included, resulting in a final sample of 260 individuals. This larger sample size reduces the risk of Type II error and enhances the robustness of the analyses.
During the data collection period, a total of 260 older adults were approached, of whom 280 agreed to participate in the study, representing an approximate response rate of 92.9%. Reasons for non-participation included lack of time, disinterest, or failure to meet inclusion criteria.
A non-probabilistic convenience sampling method was selected based on feasibility and accessibility considerations. Given the study’s observational nature, this approach efficiently facilitated the recruitment of available and willing older adults.
Inclusion criteria comprised adults aged 60 years or older without cognitive impairment (As determined by the Pfeiffer scale), and providing written informed consent. Exclusion criteria encompassed a previous suicide attempt or severe medical conditions limiting active participation (e.g., hospitalization or palliative care). Elimination criteria included study withdrawal or incomplete assessment instruments.
Instruments
The order of instrument administration was standardized to minimize participant distress, progressing from less sensitive topics (Sociodemographic data, family functionality and vulnerability to abuse) to more sensitive assessments (Attitudes toward death and suicide risk).
Sociodemographic questionnaire
A custom form designed by the authors to collect basic information, including gender, marital status, education level, and history of chronic diseases.
Suicide risk
Assessed using the Plutchik Suicide Risk Scale, a self-report instrument designed to differentiate between individuals with and without suicide risk. The scale consists of 15 items with a dichotomous response format (Yes/No). Each affirmative response scores one point; higher total scores indicate greater suicide risk, with a cut-off point established at 666. The instrument has been validated in Spanish populations, demonstrating adequate psychometric properties, including a Cronbach’s alpha of 0.89 and sensitivity and specificity values of 88%. (18).
Attitude towards death
Assessed using the Revised Profile of Attitudes toward Death (PAM-R), a multidimensional self-report scale consisting of 32 items. The PAM-R comprises four factorially derived dimensions: 1) Fear of death, 2) Approach acceptance, 3) Escape acceptance, and 4) Neutral acceptance. Responses are recorded on a Likert-type scale ranging from totally disagree to totally agree. It demonstrated a Cronbach’s alpha coefficient of 0.89 (19).
Vulnerability to abuse
Assessed using the Vulnerability to Abuse Screening Scale (VASS). The scale consists of 12 dichotomous items (Yes/No) distributed across four domains: vulnerability, dependence, dejection, and coercion. Affirmative responses are scored as one point. Higher total scores indicate greater vulnerability to abuse; a score below 6 suggests vulnerability to abuse. It demonstrated a Cronbach’s alpha coefficient of 0.77 (20).
Family functionality
Assessed with the Family APGAR (Gómez & Ponce, 2010), a 5-item scale evaluating adaptation, partnership, growth, affection, and resolution. Items are scored from 0 to 2, yielding a total score between 0 and 10. It has a reported Cronbach’s alpha of 0.84 (21).
Data collection procedure
Before starting data collection, a schedule of places to visit was compiled, including squares and public areas in the city of Saltillo, Coahuila. Older adults who met the inclusion criteria were identified, and informed consent was obtained from those who agreed to participate. Subsequently, the following instruments were administered: the sociodemographic data card, suicide risk assessment, attitude toward death scale, vulnerability to abuse scale, and finally, the family functionality assessment.
Statistical analysis
Quantitative analyses were performed using SPSS version 25. Categorical and ordinal variables were described using frequencies and percentages, while continuous variables were summarized with means, medians, and standard deviations. The Kolmogorov–Smirnov test indicated that the continuous data did not follow a normal distribution; therefore, Spearman’s rank correlation coefficient was utilized for bivariate analyses.
To address the primary objective, a multiple linear regression model was fitted to estimate the explained variance (R2) and identify the predictive contribution of each independent variable toward suicide risk. This model provides standardized beta coefficients to indicate the direction and strength of associations, thereby clarifying the impact of the investigated psychosocial factors.
Results
The sample consisted of 260 older adults, whose ages ranged from 60 to 89 (69.25±6.80 years). The majority were women, possessed a secondary education, were married, and reported no chronic diseases (Table 1).
As shown in Table 2, risk of suicide was present in 13.8 (n=36) of the participants. Furthermore, vulnerability to abuse had a prevalence of 10.0% (n=26). Regarding family dynamics, moderate to severe dysfunctionality was reported by 33.9% (n=88) of the sample. Finally, attitudes towards death were generally ambivalent (i.e., demonstrating both acceptance and rejection).
As presented in Table 3, there was a significant positive correlation between age and suicide risk (r = 0.194, p = 0.002). Suicide risk also showed a significant positive correlation with vulnerability to abuse (r = 0.221, p < 0.001) and a significant negative correlation with family functionality (r = -0.380, p < 0.001), the latter being the strongest association in the model. Additionally, higher family functionality was significantly correlated with a less positive attitude toward death (r = -0.135, p = 0.019) and lower vulnerability to abuse (r = -0.282, p < 0.001).
The multiple linear regression model was statistically significant (F = 13.457, p < 0.001) and explained 17.4% of the variance in suicide risk (adjusted R² = 0.174). Among all predictors, family functionality (β = -0.350, p < 0.001) was the strongest and only significant independent predictor, accounting for the largest unique contribution to the model. (Table 4).
|
Table 1. Sociodemographic data of older adults (n=260)
 |
|
Table 2. Description of invisible factors and suicide risk (n=260)
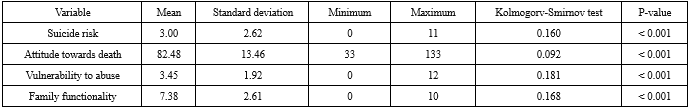 Table 3. Spearman's rank correlation coefficient of independent variables with suicide risk (n=260) 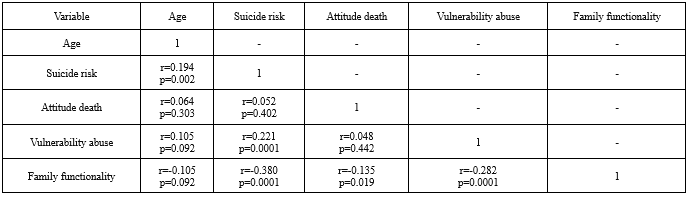 r= Correlation Coefficient, p < 0.05 is statistically significant Table 4. Influence of invisible factors on the risk of suicide in older adults 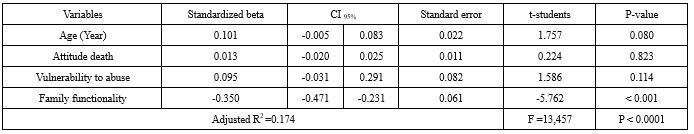 |
Discussion
The objective of this study was to determine the explanatory power of the attitudes towards death, vulnerability to abuse, and family functionality on suicide risk in older adults. The results confirm that suicidal behavior in old age is a multidimensional phenomenon, in which individual, relational, and contextual factors converge, with family functionality being the element with the greatest explanatory weight.
Descriptively, a notable proportion of older adults presented a risk of suicide, even though the majority were married and without chronic diseases. This coincides with previous studies indicating that suicidal risk in old age does not depend exclusively on physical illness, but also on less visible psychosocial conditions (6,22). This finding reinforces the need to analyze suicide in older adults beyond the traditional biomedical model.
Regarding attitude towards death, the results indicate an ambivalent posture characterized by the coexistence of acceptance and rejection. This pattern has been documented in previous research, which shows that, although older people may show acceptance of the life cycle and death as a natural event, fears associated with suffering, dependence, and loss of control persist (11,23). The absence of a significant correlation between the attitudes towards death and the risk of suicide suggests that this variable, by itself, does not constitute a direct risk factor, but rather its influence could be mediated by other elements, such as family functionality or the presence of abuse.
Regarding vulnerability to abuse, a positive and significant correlation was identified with suicide risk, which confirming its relevance as a psychosocial risk factor. International research has shown that abuse, even in its less visible forms such as emotional neglect or coercion, increases suicidal ideation by generating feelings of helplessness, humiliation, and hopelessness in older adults (24). The observed correlation supports the usefulness of the VASS scale as an early detection instrument, as it facilitates the identification of risk conditions before abuse becomes explicit (25).
A central finding of the study was the inverse relationship between family functionality and suicide risk, as well as its negative association with vulnerability to abuse. These results align with the literature, which positions the family as a fundamental axis in protecting mental health in old age. A functional family fosters communication, emotional support, and effective conflict resolution, factors that decrease the chance of self-destructive behaviors (16,26).
The correlational analysis also showed that the older you are, the greater the risk of suicide and lower family functionality, which coincides with research that indicates that advanced aging can imply a progressive reduction in support networks, greater dependency, and increased perception of burden, especially in fragile family contexts (3). This finding reinforces the importance of considering age not only as a chronological variable but as a marker of accumulated social vulnerability.
The multiple linear regression model showed that the variables analyzed explained 17.4% of the variance in suicide risk. This figure aligns with previous research in elderly populations where psychosocial factors tend to have moderate yet meaningful explanatory power. Within the model, family functioning was the only significant predictor, highlighting its important protective role against suicide risk. The lack of significance of attitude toward death and vulnerability to abuse in the final model were not statistically significant. Their effects might be influenced or moderated by family functioning, indicating that family dynamics play a key regulatory role.
From the perspective of collective health, these results confirm that the risk of suicide in older adults cannot be understood as an isolated individual phenomenon, but as the result of social, family, and symbolic processes that accumulate throughout the life course. Family functionality acts as a structural factor affecting both abuse exposure and how death and aging are perceived and reinterpreted. In this sense, the findings provide evidence for the design of prevention strategies that strengthen family and community networks and for the early detection of situations of social vulnerability (27).
A study argues that culture influences perceptions of death and suicide through shared beliefs, values, and meanings that shape how individuals interpret suffering, hopelessness, and the meaning of life; therefore, culture may act as a protective factor against suicide risk (28). Paphitis and cols indicate that domestic abuse is an important risk factor for suicide. Similarly, the present study found a relationship between abuse and suicide risk; however, it was not identified as a predictive factor, although it was associated with an increased risk (29).
Family functioning was identified as a predictive factor in this study, consistent with evidence indicating that, in Latino populations, family may constitute a risk factor for suicidal behavior when dysfunctional family dynamics, abuse, substance use, or limited emotional support are present, thereby increasing psychological vulnerability and suicide risk (30).
The present study has limitations that should be considered when interpreting the results. Its cross-sectional design does not allow establishing causal relationships between variables and limits the analysis to identifying associations. The non-probabilistic convenience sampling restricts the generalizability of the findings to the older adult population as a whole, as the sample was obtained exclusively in the city of Saltillo, Coahuila. Additionally, the use of self-report instruments may have introduced social desirability bias, particularly in sensitive variables such as suicide risk and vulnerability to abuse. Finally, the moderate explanatory capacity of the model suggests the influence of other factors not considered in this study.
It is recommended to systematically incorporate the assessment of family functioning and vulnerability to abuse into primary and community care for older adults as part of suicide prevention strategies. Strengthening the training of healthcare personnel in the early detection of psychosocial risk factors with a collective health approach is necessary. Likewise, future research is encouraged to use longitudinal designs and probabilistic sampling, include additional variables, and consider qualitative methodologies that allow for a deeper exploration of the subjective experiences of aging and suicide risk.
Conclusion
The findings of this study confirm that suicide risk in older adults is a multifactorial phenomenon influenced by psychosocial and family-related variables. Among the factors analyzed, family functionality emerged as the only significant predictor and the variable with the greatest explanatory weight, demonstrating an inverse relationship with suicide risk and vulnerability to abuse. While vulnerability to abuse correlated positively with suicide risk, it was not a significant predictor in the multivariate model. Likewise, attitude toward death presented an ambivalent pattern and did not demonstrate predictive capacity. Overall, the explanatory model accounted for 17.4% of the variance in suicide risk, highlighting the relevance of relational and contextual factors in late adulthood.
From an applied perspective, these results underscore the importance of strengthening family environments as a key strategy for suicide prevention in older adults. Interventions should prioritize early detection of family dysfunction and vulnerability to abuse, incorporating screening tools into primary health care and community programs. Public health policies should promote family-based and community-based support networks, foster social inclusion, and enhance multidisciplinary strategies aimed at protecting the mental health of older adults. Effectively addressing suicide risk from a collective health perspective necessitates integrating psychosocial assessment into routine geriatric care and strengthening protective family dynamics.
Future research should explore additional psychosocial, cultural, and structural variables that may increase the explanatory capacity of suicide risk models in older populations. Longitudinal studies are recommended to better understand causal relationships and temporal dynamics among family functioning, abuse vulnerability, and suicide risk. Furthermore, qualitative approaches could provide deeper insight into the subjective experiences of older adults, contributing to the development of more culturally sensitive and context-specific prevention strategies.
Acknowledgement
The valuable participation of the older adults who took part in the study is acknowledged, as well as the collaboration of the research team in data collection.
Funding Sources
Not applicable
Ethical Statement
This study complied with the provisions of the General Health Law on Health Research in Mexico and the Official Mexican Standard (31) NOM-012-SSA3-2012 for research involving human participants. Ethical approval was obtained from the Ethics Committee of the Contemporary University of the Americas. The official ethics approval reference number assigned by the Ethics Committee is: EAD12021-030.
Written informed consent was obtained from all participants prior to data collection. Participants were informed about the study objectives, the voluntary nature of participation, confidentiality measures, and their right to withdraw at any time. Due to the sensitive nature of the study, data collection was conducted by trained personnel capable of identifying emotional distress; assessments were paused or discontinued according to participants’ preferences. When suicide risk was identified, a referral protocol was activated to provide immediate guidance and referral to local mental health services for professional evaluation and follow-up. All collected information was anonymized and handled confidentially.
Conflicts of Interest
The Authors declares that there is no conflict of interest.
Author Contributions
IAMF and DCP conceptualized and designed the study. ART contributed to data collection and preliminary analysis. JAMF performed statistical analyses and contributed to the interpretation of results. KPVG provided critical insights and supervised the research methodology. IAMF and ALCC provided overall project supervision, drafted the manuscript, and coordinated revisions. All authors reviewed, edited, and approved the final version of the manuscript.
Data Availability Statement
The datasets generated and/or analyzed during the present study are not publicly available due to confidentiality and ethical restrictions.
Use of Artificial Intelligence
AI-assisted tools were used to support language editing; these tools were not involved in data analysis, the writing of scientific content, the interpretation of results, or scientific decision-making.
Type of study: Original Article |
Subject:
Psychology and Psychiatry
References
1. Organización Mundial de la Salud. Envejecimiento y salud [Internet]. Ginebra: OMS; 2024 [citado 2025 septiembre 6]. Disponible en: https://www.who.int/es/news-room/fact-sheets/detail/ageing-and-health [View at Publisher]
2. Ortiz J, Núñez R, Rosales A, Sánchez F. Vivir más: vivir mejor. Estrategia psicosocial para el cuidado integral de la persona mayor. Derecho Realidad. 2018;16(31):151-61. [View at Publisher] [DOI] [Google Scholar]
3. Velásquez Suarez JM. Suicidio en el anciano Suicide in the Elderly. Rev Colomb Psiquiatr. 2013;43(1):80-4. [View at Publisher] [DOI] [PMID] [Google Scholar]
4. Instituto Nacional de las Personas Adultas Mayores. Cambios psicosociales del envejecimiento [Internet]. México: INAPAM; 2019 [citado 2026 febrero 6]. Disponible en: https://www.gob.mx/inapam. [View at Publisher]
5. Laínez S, Carbonell A, Yus R, Melendéz E, Marzal Á. El suicidio en personas mayores. Rev Sanit Investig. 2022;3(2):12. [View at Publisher] [Google Scholar]
6. Estadella C, Medina C, Toro C. Muertes por suicidio en personas mayores y género masculino en Chile. Rev Chil Neuropsiquiatr. 2023;61(4):393-401. [View at Publisher] [DOI] [Google Scholar]
7. Instituto Nacional de las Personas Adultas Mayores. 10 de septiembre: Día Mundial de la Prevención del Suicidio [Internet]. México: INAPAM; 2019 [citado 2025 septiembre 7]. Disponible en: https://www.gob.mx/inapam [View at Publisher]
8. Organización Mundial de la Salud. Suicidio [Internet]; 2025 [citado 24 feb 2026]. Disponible en: https://www.who.int/es/news-room/fact-sheets/detail/suicide [View at Publisher]
9. Instituto Nacional de Estadística y Geografía. Estadísticas a propósito del Día Mundial para la Prevención del Suicidio [Internet]. 2025 [citado 24 feb 2026]. Disponible en: https://www.inegi.org.mx/contenidos/saladeprensa/aproposito/2025/EAP_Suicidio_25.pdf [View at Publisher]
10. Durán-Badillo T, Maldonado M, Martínez ML, Gutiérrez G, Ávila H. Miedo ante la muerte y calidad de vida en adultos mayores. Rev Enferm Salud. 2020;19(2):123-31. [View at Publisher] [DOI] [Google Scholar]
11. Sekowski M. Attitude toward death from the perspective of Erikson's psychosocial development An Unused Potential. Omega (Westport). 2022;84(3):935-57. [View at Publisher] [DOI] [PMID] [Google Scholar]
12. Moreno Jurado CI. Actitud ante la muerte y conductas de riesgo en alumnos de una universidad pública en el estado de México. Persona. 2019;22(1):53-65. [View at Publisher] [DOI] [Google Scholar]
13. Grover S, Verma M, Singh T, Dahiya N, Nehra R. Elder abuse and suicidal behavior in older adults. J Elder Abuse Negl. 2021;33(4):289-305. [DOI] [PMID]
14. Mendonca C, De Leo D, Ivbijaro G, Svab I. Loneliness and abuse as risk factors for suicide in older adults: new developments and the contribution of the WPA Section on Old Age Psychiatry. World Psychiatry. 2021;20(3):455-6. [View at Publisher] [DOI] [PMID] [Google Scholar]
15. Cortaza-Ramírez L, Blanco-Enríquez F, Hernández-Cortaza BA, Lugo-Ramírez LA, Beverido Sustaeta P, Salas B, et al. Uso de internet, consumo de alcohol y funcionalidad familiar en adolescentes mexicanos. Health and Addictions/Salud Y Drogas. 2019;19(2):59–69. [View at Publisher] [DOI] [Google Scholar]
16. Reyes Narváez SE, Oyola Canto MS. Funcionalidad familiar y conductas de riesgo en estudiantes universitarios de ciencias de la salud. Comuni@cción. 2022;13(2):127-37. [View at Publisher] [DOI] [Google Scholar]
17. Grove SK, Gray JR. Investigación en enfermería. 7ª ed. Barcelona: Elsevier; 2019. [View at Publisher] [Google Scholar]
18. Suárez-Colorado Y, Palacio-Sañudo J, Caballero-Domínguez CC, Pineda-Roa CA. Adaptación, validez de constructo y confiabilidad de la escala de riesgo suicida Plutchik en adolescentes colombianos. Rev Latinoam Psicol. 2019;51(3):145-52. [View at Publisher] [DOI]
19. Río-Valle Schmidt J.Validación de la versión española de la "escala de Bugen de afrontamiento de la muerte" y del "perfil revisado de actitudes hacia la muerte": estudio comparativo y transcultural. Puesta en marcha de un programa de intervención. Granada: Editorial Universidad de Granada; 2007. [View at Publisher] [Google Scholar]
20. Schofield MJ, Mishra GD. Validity of self-report screening scale for elder abuse: Women's Health Australia Study. Gerontologist. 2003;43(1):110-20. [View at Publisher] [DOI] [PMID] [Google Scholar]
21. Gómez-Clavelina FJ, Ponce-Rosas ER. Una nueva propuesta para la interpretación del Family apgar (versión en español). Rev Med La Paz. 2010;17(14):14-18. [View at Publisher] [DOI]
22. Sobering, J., Brady, A.J., Brown, L.M. Suicide and Older Adults: The Role of Risk and Protective Factors. In: Pompili, M. (eds) Suicide Risk Assessment and Prevention. Springer, Cham. 2021.p. 1-16. [View at Publisher] [DOI] [Google Scholar]
23. Durán-Badillo T, Maldonado M, Martínez ML, Gutiérrez G, Ávila H, López SJ. Fear of death and quality of life in older adults. Enferm Glob. 2020;19(2):296-304. [View at Publisher] [DOI] [Google Scholar]
24. Grover S, Verma M, Singh T, Dahiya N, Nehra R. Screening for abuse of older adults : A Study Done at Primary Health Care Level in Punjab, India. Indian J Psychol Med. 2021;43(4):312-8. [View at Publisher] [DOI] [PMID] [Google Scholar]
25. Filipska K, Biercewicz M, Wiśniewski A, Kędziora-Kornatowska K, Ślusarz R. Reliability and validity of the polish version of the vulnerability to Abuse Screening Scale (VASS). J Elder Abuse Negl. 2022;34(1):56-69. [View at Publisher] [DOI] [PMID] [Google Scholar]
26. Cortaza-Ramírez L, Blanco-Enríquez F, Hernández-Cortaza BA, Lugo-Ramírez LA, Sustaeta PB, Salas B, et al. Uso de internet, consumo de alcohol y funcionalidad familiar en adolescentes mexicanos. Health Addict. 2019;19(2):59-69. [View at Publisher] [DOI] [Google Scholar]
27. Torres Guarín YA. El enfoque de capacidades y el derecho a la ciudad: una mirada desde el envejecimiento y la vejez [tesis de maestría]. México: FLACSO; 2019. [View at Publisher] [Google Scholar]
28. Kirmayer LJ. Suicide in cultural context: An ecosocial approach. Transcult Psychiatry. 2022;59(1):3-12. [View at Publisher] [DOI] [PMID] [Google Scholar]
29. Keynejad RC ,Paphitis S, Davidge S, Jacob S, Howard LM. Domestic abuse is an important risk factor for suicide. BMJ. 2022;379:o2890. [View at Publisher] [DOI] [PMID] [Google Scholar]
30. Chan Coob JG, Santoyo Manzanilla DDJ, Ordaz Cuevas AA. Family factors as a risk factor for suicide in people in residential treatment for substance use. Rev Int Investig Adicciones. 2025;11(1):1-9. [View at Publisher] [DOI] [Google Scholar]
31. Diario Oficial de la Federación. Reglamento de la Ley General de Salud en materia de investigación para la salud [Internet]. México; 2014 [citado 2025 septiembre 18]. Disponible en: https://www.diputados.gob.mx [View at Publisher]
Send email to the article author
| Rights and permissions | |
 |
This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License. |
