
Volume 23, Issue 2 (6-2026)
J Res Dev Nurs Midw 2026, 23(2): 18-23 |
Back to browse issues page


Download citation:
BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:


BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:
Iran A, Aghahosseini S S, Nazli R, Abbas S, Ahsan F. Effect of nursing care based on Roy’s Adaptation Model on pain severity in intensive care unit patients in Pakistan. J Res Dev Nurs Midw 2026; 23 (2) :18-23
URL: http://nmj.goums.ac.ir/article-1-2309-en.html
URL: http://nmj.goums.ac.ir/article-1-2309-en.html


1- Lahore School of Nursing, The University of Lahore, Lahore, Pakistan
2- Lahore School of Nursing, The University of Lahore, Lahore, Pakistan ,farnazahsan562@gmail.com
2- Lahore School of Nursing, The University of Lahore, Lahore, Pakistan ,
Full-Text [PDF 484 kb]
(437 Downloads)
| Abstract (HTML) (1718 Views)
Discussion
The present study examined the effect of the Roy Adaptation Model on pain levels among patients admitted to the intensive care unit. The findings indicate that nursing care based on the Roy Adaptation Model may help reduce pain and support patient adaptation in this population.
The experience of pain is often accompanied by fear, anxiety, and stress (14-16). Several non-pharmacological interventions, such as distraction techniques, physical and psychological relaxation, guided imagery, and cutaneous stimulation, provide adaptive strategies that can reduce pain perception and make pain more tolerable (17-19). Previous studies have recommended the Roy Adaptation Model because of its positive and effective impact on patients (20-22). Roy emphasizes that physiological adaptation is one of the key factors contributing to the reduction of disease-related complications (23-25).
The findings of the present study indicated that the intervention was associated with a gradual reduction in pain scores, particularly during nighttime assessments. These results suggest that non-pharmacological pain-relief methods, including nursing care models such as the Roy Adaptation Model, are effective in reducing pain, particularly among ICU patients (26,27). The findings of the present study are consistent with those of Richard-Lalonde et al., who conducted a systematic review and meta-analysis of 18 randomized controlled trials involving adult ICU patients. They reported that music interventions significantly reduced pain intensity, with sessions lasting 20-30 minutes producing the greatest analgesic effect. The authors concluded that music is an effective non-pharmacological adjunct to pain management in critically ill patients (28).
Similarly, Sandvik et al., in a scoping review of non-pharmacological pain interventions in intensive care units, concluded that non-pharmacological nursing interventions can complement pharmacological analgesia by reducing pain, improving patient comfort, and potentially decreasing analgesic requirements. They emphasized that such interventions are safe, inexpensive, and should be integrated into routine ICU nursing care (29).
More recently, Avcı and Kaplan Serin conducted a systematic review of mechanically ventilated ICU patients and found that, across ten studies involving 603 patients, music interventions consistently reduced pain without causing adverse effects. The authors recommended incorporating music as a routine nursing intervention for mechanically ventilated patients because of its safety, feasibility, and effectiveness in pain reduction (30).
The reduction in pain observed in the present study may be explained by the physiological adaptation mechanisms emphasized in the Roy Adaptation Model. Within the physiological mode, nursing interventions focused on improving sleep, nutrition, relaxation, respiratory function, and overall physical stability. These interventions may reduce stress responses, improve physiological resilience, and enhance tissue oxygenation, thereby decreasing pain perception and contributing to the lower pain scores observed in the intervention group.
Therefore, the findings of the present study, together with previous evidence, suggest that the Roy Adaptation Model may reduce pain by improving physiological adaptation. By addressing modifiable physiological needs such as sleep, nutrition, relaxation, and respiratory care, this model may reduce stress responses and improve physiological stability, thereby decreasing pain perception in critically ill patients. These findings support its use as a complementary, non-pharmacological approach to pain management in intensive care units.
Although statistically significant reductions in pain scores were observed, the effect sizes were small (η² = 0.021-0.040), indicating modest intervention effects. Nevertheless, as the Roy Adaptation Model is a safe and low-cost non-pharmacological nursing intervention, even small reductions in pain may be clinically valuable as an adjunct to pharmacological analgesia in ICU patients. However, because analgesic consumption, ICU length of stay, and other clinical outcomes were not assessed, the clinical significance of these findings should be interpreted with caution.
Despite the valuable findings of this study, several limitations should be acknowledged. The study was conducted in a single hospital, which may limit the generalizability of the results to other clinical settings or patient populations. The relatively small sample size may have affected the statistical power of the study. Because patients were unable to self-report, pain assessment was based on observational measures that are inherently subjective and may be influenced by evaluator judgment, individual psychological conditions, level of consciousness, or environmental factors in the ICU. As the study was conducted in a single hospital, contamination between the intervention and control groups may have occurred through interactions among healthcare staff. Sedation level was not assessed using a standardized scale (e.g., RASS), which may have influenced Behavioral Pain Scale (BPS) scores. In addition, the short follow-up period limited the evaluation of the long-term effects of the Roy Adaptation Model-based intervention on pain outcomes. Furthermore, because clinically relevant outcomes such as analgesic requirements, opioid consumption, duration of mechanical ventilation, and ICU length of stay were not assessed, the clinical implications of the observed pain reduction could not be fully determined. Therefore, future studies with larger sample sizes, multicenter designs, and longer follow-up periods are recommended to confirm and extend these findings. The study may have been underpowered to detect small to moderate between-group differences, particularly given the relatively small effect sizes observed. Therefore, the possibility of type II error should be considered when interpreting the non-significant findings across most time points.
Conclusion
The findings of this study suggest that nursing care based on the Roy Adaptation Model, particularly interventions targeting the physiological mode, may be associated with a gradual reduction in pain among patients admitted to the intensive care unit. These findings support the potential value of incorporating theory-based nursing interventions into ICU practice to promote physiological adaptation and improve pain management. However, given the relatively small effect sizes and limited between-group differences observed at individual time points, the findings should be interpreted with caution. If confirmed in future studies, this theory-based approach may provide nurses with a structured framework for planning and delivering individualized pain-management interventions in intensive care settings. Further multicenter studies with larger sample sizes, longer follow-up periods, and more rigorous designs are warranted to confirm the potential effectiveness and generalizability of interventions based on the Roy Adaptation Model in critical care settings.
Acknowledgement
The authors would like to express their sincere gratitude to all intensive care unit nurses for their valuable cooperation and assistance in conducting this study.
Funding Sources
The authors declared that this study received no financial support.
Ethical Statement
This study was conducted in accordance with ethical principles for research involving human participants. All participants provided written informed consent after receiving full explanations of the study objectives, procedures, potential benefits, and risks. For patients with reduced consciousness (GCS≤7), informed consent was obtained from the patient’s legally authorized representative or next of kin. Patient confidentiality was strictly maintained, and the data were used solely for research purposes. The study protocol was approved by the Institutional Research Ethics Board of the University of Lahore (UOL/IREB/26/17/03/04), and all procedures were carried out in accordance with the Declaration of Helsinki.
Conflicts of Interest
The authors have no conflicts of interest to declare.
Author Contributions
Concept: F.A; Design: Sh.S.A; Supervision: Sh.S.A; Resources: A.I; Data collection and/or Processing: S.A; Analysis and/or Interpretation: Sh.S.A; Literature search: R.N; Manuscript writing: Sh.S.A; Critical review: Sh.S.A;
Data Availability Statement
Data will be available upon reasonable request, subject to review by the research team and consideration of data confidentiality.
Use of Artificial Intelligence
No AI tools were used during the preparation of this work.
Full-Text: (180 Views)
Introduction
Pain is an unpleasant physical and psychological experience and a complex phenomenon considered one of the most common symptoms among patients hospitalized in intensive care units (ICUs) (1). Various studies have shown that a high percentage of ICU patients experience different degrees of pain during hospitalization (2). Pain is now considered sufficiently important that its assessment and documentation are regarded as essential as the recording of vital signs. If pain is not properly monitored and managed, it can lead to serious complications affecting multiple body systems (3).
Untreated pain endangers the patient’s condition and increases activation of the neuroendocrine and sympathetic systems, accompanied by tachycardia, increased myocardial oxygen demand, immune system suppression, increased blood coagulability, an elevated metabolic rate, and restricted movement. These changes may subsequently lead to pulmonary complications, decreased gastrointestinal activity, and an impaired level of consciousness (4). Inadequate pain management also increases the length of hospital stay, readmission rates, and patient dissatisfaction with medical care, ultimately contributing to morbidity and increased mortality (5).
Therefore, appropriate pain management requires repeated pain assessments and individualized treatment based on careful observation of the patient’s condition. Pain management is one of the most essential components of patient care, and nurses play a key role in this process (6). Few nursing interventions are more important than pain relief. Effective pain management is particularly challenging in ICUs, where many patients are unable to communicate their pain, and depends on systematic and accurate pain assessment to guide clinical decision-making and the use of analgesic medications. Consequently, nurses must possess sufficient knowledge and skills to assess pain, understand its effects on patients, apply pain-relief methods, and evaluate the effectiveness of these interventions (7).
One approach to pain reduction involves the use of nursing models, through which health can be promoted by facilitating adaptation across different dimensions of the patient’s existence (8). As a nursing framework, the Roy Adaptation Model emphasizes the assessment of stimuli, the identification of maladaptive behaviors, and the transformation of these behaviors into adaptive responses, thereby playing a significant role in health promotion. Applying this model enhances the focus, organization, and direction of nurses’ thoughts and actions toward desired goals in a more effective and appropriate manner (9).
According to this model, nurses systematically and accurately assess patients through interviews, observation, and measurement. Maladaptive behaviors, which represent patients’ problems, are identified together with their related stimuli across four adaptive modes; specific educational and care plans are then designed to resolve these problems and promote adaptive behaviors (10). Roy conceptualizes adaptation as occurring in four modes: physiological, self-concept, role function, and interdependence. The physiological mode is primarily responsible for maintaining physiological balance in relation to basic needs such as activity and rest, nutrition, elimination, oxygenation, and protection (11).
Some researchers have implemented interventions based on all dimensions of the Roy Adaptation Model, whereas others have targeted only selected dimensions, depending on patient conditions and environmental factors (12). Therefore, the present study aimed to determine the effect of the Roy Adaptation Model on pain intensity in patients admitted to the intensive care unit.
Methods
This quasi-experimental study was conducted in 2026 among 100 patients admitted to the ICU of Teaching Hospital, Lahore, affiliated with the University of Lahore, Pakistan. The inclusion criteria were age over 18 years, a baseline Behavioral Pain Scale (BPS) score indicating the presence of pain (BPS ≥ 4), and no history of psychiatric illness. For patients with reduced consciousness (GCS≤7), informed consent was obtained from the patient’s legally authorized representative or next of kin. The exclusion criteria were patient death during the study, transfer to another ward within 24 hours, receipt of neuromuscular blocking agents, and unwillingness to continue participation.
The sample size was calculated using the formula for comparing the means of two independent groups, assuming a two-sided significance level of 0.05 (α = 0.05), a statistical power of 80% (β = 0.20), and the expected means and standard deviations obtained from a previous study (9). To account for a potential 10% attrition rate, the sample size was increased to 50 participants per group.
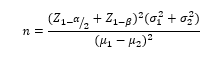
Initially, two comparable ICU wards were selected. Before participant recruitment, the two wards were randomly assigned to either the intervention or control group using a simple lottery conducted by an independent researcher who was not involved in participant recruitment, intervention delivery, or outcome assessment. Following this allocation, all eligible patients admitted to each ward were consecutively recruited according to the predefined inclusion criteria. Patients were assigned to the intervention or control group based solely on the ICU ward to which they were routinely admitted as part of the hospital admission process. The research team had no role in determining patients’ ward admission and did not transfer patients between wards for study purposes. Because the intervention was delivered at the ward level to minimize contamination between participants, individual patient randomization was not feasible; therefore, the study used a quasi-experimental design. Outcome assessments were performed by trained research nurses who were independent of the intervention team and blinded to group allocation. The outcome assessors had no role in delivering the intervention, and pain was assessed using the Behavioral Pain Scale (BPS) according to a standardized assessment protocol.
The study procedure involved providing four in-ward training sessions for nurses in the intervention ward on care based on the Roy Adaptation Model. Each session lasted approximately 60-90 minutes and covered the theoretical concepts of the model and their application to ICU nursing care. The training content was developed from standard literature and reviewed for content validity by five faculty members with expertise in nursing education and critical care nursing, including two Associate Professors and three Assistant Professors. Nurses’ competency was assessed after training using a structured evaluation checklist and return demonstration of key concepts. To ensure intervention fidelity, adherence to the Roy Adaptation Model was monitored using a standardized checklist completed by the researcher during clinical supervision visits. Regular supervision and feedback sessions were also conducted throughout the intervention period to ensure consistent application of the model.
Because of the patients’ varying levels of consciousness, complete dependence on care, and physical limitations, assessment of the three dimensions of role function, self-concept, and independence/dependence was not feasible. Therefore, this study focused on evaluating patients’ maladaptive behaviors in the physiological dimension. Nurses attempted to transform maladaptive behaviors into adaptive behaviors across seven physiological dimensions by increasing, decreasing, or modifying specific stimuli. These dimensions included fluid and electrolyte balance; nutrition; sleep and rest; activity and mobility; elimination; oxygenation and circulatory status; and endocrine function. The interventions in each dimension were as follows:
The intervention was implemented according to the Roy Adaptation Model by identifying focal, contextual, and residual stimuli related to pain and applying individualized nursing interventions to promote adaptive responses.
Pain is an unpleasant physical and psychological experience and a complex phenomenon considered one of the most common symptoms among patients hospitalized in intensive care units (ICUs) (1). Various studies have shown that a high percentage of ICU patients experience different degrees of pain during hospitalization (2). Pain is now considered sufficiently important that its assessment and documentation are regarded as essential as the recording of vital signs. If pain is not properly monitored and managed, it can lead to serious complications affecting multiple body systems (3).
Untreated pain endangers the patient’s condition and increases activation of the neuroendocrine and sympathetic systems, accompanied by tachycardia, increased myocardial oxygen demand, immune system suppression, increased blood coagulability, an elevated metabolic rate, and restricted movement. These changes may subsequently lead to pulmonary complications, decreased gastrointestinal activity, and an impaired level of consciousness (4). Inadequate pain management also increases the length of hospital stay, readmission rates, and patient dissatisfaction with medical care, ultimately contributing to morbidity and increased mortality (5).
Therefore, appropriate pain management requires repeated pain assessments and individualized treatment based on careful observation of the patient’s condition. Pain management is one of the most essential components of patient care, and nurses play a key role in this process (6). Few nursing interventions are more important than pain relief. Effective pain management is particularly challenging in ICUs, where many patients are unable to communicate their pain, and depends on systematic and accurate pain assessment to guide clinical decision-making and the use of analgesic medications. Consequently, nurses must possess sufficient knowledge and skills to assess pain, understand its effects on patients, apply pain-relief methods, and evaluate the effectiveness of these interventions (7).
One approach to pain reduction involves the use of nursing models, through which health can be promoted by facilitating adaptation across different dimensions of the patient’s existence (8). As a nursing framework, the Roy Adaptation Model emphasizes the assessment of stimuli, the identification of maladaptive behaviors, and the transformation of these behaviors into adaptive responses, thereby playing a significant role in health promotion. Applying this model enhances the focus, organization, and direction of nurses’ thoughts and actions toward desired goals in a more effective and appropriate manner (9).
According to this model, nurses systematically and accurately assess patients through interviews, observation, and measurement. Maladaptive behaviors, which represent patients’ problems, are identified together with their related stimuli across four adaptive modes; specific educational and care plans are then designed to resolve these problems and promote adaptive behaviors (10). Roy conceptualizes adaptation as occurring in four modes: physiological, self-concept, role function, and interdependence. The physiological mode is primarily responsible for maintaining physiological balance in relation to basic needs such as activity and rest, nutrition, elimination, oxygenation, and protection (11).
Some researchers have implemented interventions based on all dimensions of the Roy Adaptation Model, whereas others have targeted only selected dimensions, depending on patient conditions and environmental factors (12). Therefore, the present study aimed to determine the effect of the Roy Adaptation Model on pain intensity in patients admitted to the intensive care unit.
Methods
This quasi-experimental study was conducted in 2026 among 100 patients admitted to the ICU of Teaching Hospital, Lahore, affiliated with the University of Lahore, Pakistan. The inclusion criteria were age over 18 years, a baseline Behavioral Pain Scale (BPS) score indicating the presence of pain (BPS ≥ 4), and no history of psychiatric illness. For patients with reduced consciousness (GCS≤7), informed consent was obtained from the patient’s legally authorized representative or next of kin. The exclusion criteria were patient death during the study, transfer to another ward within 24 hours, receipt of neuromuscular blocking agents, and unwillingness to continue participation.
The sample size was calculated using the formula for comparing the means of two independent groups, assuming a two-sided significance level of 0.05 (α = 0.05), a statistical power of 80% (β = 0.20), and the expected means and standard deviations obtained from a previous study (9). To account for a potential 10% attrition rate, the sample size was increased to 50 participants per group.
Initially, two comparable ICU wards were selected. Before participant recruitment, the two wards were randomly assigned to either the intervention or control group using a simple lottery conducted by an independent researcher who was not involved in participant recruitment, intervention delivery, or outcome assessment. Following this allocation, all eligible patients admitted to each ward were consecutively recruited according to the predefined inclusion criteria. Patients were assigned to the intervention or control group based solely on the ICU ward to which they were routinely admitted as part of the hospital admission process. The research team had no role in determining patients’ ward admission and did not transfer patients between wards for study purposes. Because the intervention was delivered at the ward level to minimize contamination between participants, individual patient randomization was not feasible; therefore, the study used a quasi-experimental design. Outcome assessments were performed by trained research nurses who were independent of the intervention team and blinded to group allocation. The outcome assessors had no role in delivering the intervention, and pain was assessed using the Behavioral Pain Scale (BPS) according to a standardized assessment protocol.
The study procedure involved providing four in-ward training sessions for nurses in the intervention ward on care based on the Roy Adaptation Model. Each session lasted approximately 60-90 minutes and covered the theoretical concepts of the model and their application to ICU nursing care. The training content was developed from standard literature and reviewed for content validity by five faculty members with expertise in nursing education and critical care nursing, including two Associate Professors and three Assistant Professors. Nurses’ competency was assessed after training using a structured evaluation checklist and return demonstration of key concepts. To ensure intervention fidelity, adherence to the Roy Adaptation Model was monitored using a standardized checklist completed by the researcher during clinical supervision visits. Regular supervision and feedback sessions were also conducted throughout the intervention period to ensure consistent application of the model.
Because of the patients’ varying levels of consciousness, complete dependence on care, and physical limitations, assessment of the three dimensions of role function, self-concept, and independence/dependence was not feasible. Therefore, this study focused on evaluating patients’ maladaptive behaviors in the physiological dimension. Nurses attempted to transform maladaptive behaviors into adaptive behaviors across seven physiological dimensions by increasing, decreasing, or modifying specific stimuli. These dimensions included fluid and electrolyte balance; nutrition; sleep and rest; activity and mobility; elimination; oxygenation and circulatory status; and endocrine function. The interventions in each dimension were as follows:
The intervention was implemented according to the Roy Adaptation Model by identifying focal, contextual, and residual stimuli related to pain and applying individualized nursing interventions to promote adaptive responses.
- Activity and Mobility: Pain related to immobility and prolonged bed rest was identified as a focal stimulus. Contextual stimuli included muscle weakness and limited range of motion. Interventions included scheduled position changes every two hours, passive and active range-of-motion exercises, limb physiotherapy, and proper body alignment to reduce musculoskeletal discomfort and pain.
- Sleep and Rest: Sleep disturbance and environmental stressors were identified as contextual stimuli contributing to pain perception. Interventions included reducing environmental noise and light, scheduling nursing procedures to minimize sleep interruptions, therapeutic touch, relaxation techniques, massage, and music therapy to improve sleep quality and reduce pain-related distress.
- Nutrition: Inadequate nutritional intake was considered a contextual stimulus that could impair recovery and increase discomfort. Interventions included nutritional assessment, individualized enteral or parenteral feeding plans, caloric-intake monitoring, and collaboration with dietitians to optimize nutritional status.
- Elimination: Urinary retention, constipation, diarrhea, and discomfort associated with elimination problems were identified as focal stimuli. Interventions included regular assessment of bowel and bladder function, timely catheter care, hydration management, and measures to prevent constipation and abdominal discomfort.
- Fluid and Electrolyte Balance: Dehydration, edema, and electrolyte disturbances were identified as contextual stimuli affecting patient comfort and adaptation. Interventions included monitoring fluid intake and output, assessing laboratory values, and implementing fluid-replacement or restriction protocols as prescribed.
- Oxygenation and Circulatory Status: Dyspnea, hypoxemia, hemodynamic instability, and discomfort associated with mechanical ventilation were identified as focal stimuli contributing to pain and stress. Interventions included continuous monitoring of oxygen saturation and vital signs, optimizing patient positioning, ensuring ventilator synchrony, airway care, and prompt management of abnormalities in oxygenation and circulation.
- Endocrine and Metabolic Function: Fever, metabolic disturbances, and endocrine alterations were identified as contextual stimuli that could intensify discomfort and pain perception. Interventions included monitoring body temperature and metabolic indicators, implementing fever-control measures, and collaborating with physicians to manage endocrine abnormalities.
Routine care in the control group was provided by ICU nurses and included executing physician orders, daily evaluation of consciousness levels, systematic patient assessment, and hemodynamic monitoring. Medical or nursing interventions were applied as needed without using nursing models. Data on potential confounding factors, including the use of narcotics and sedatives, were collected in both groups and considered in the analysis.
Patient pain was measured in both groups twice daily over seven days, in the morning (6:00-9:00) and evening (18:00-21:00). Data-collection tools included demographic characteristics form and the Behavioral Pain Scale (BPS). This scale is an observational tool used to assess pain in critically ill and mechanically ventilated patients who are unable to self-report. The scale includes three behavioral subscales: facial expression, upper-limb movements, and compliance with ventilation. Each subscale is scored from 1 to 4. The total BPS score ranges from 3 to 12, with higher total scores indicating more severe pain. Its validity has been established through content and construct validation in previous studies (13). The reliability of the Behavioral Pain Scale has also been reported in previous research using inter-rater and intra-rater agreement, demonstrating high reliability. In the present study, inter-rater reliability was additionally assessed to ensure measurement consistency in the ICU setting (ICC = 0.94).
Because the patients had impaired levels of consciousness and were unable to self-report pain, pain was assessed using the Behavioral Pain Scale (BPS), a validated observational instrument for critically ill patients. To ensure standardized and consistent assessments, the BPS was administered according to a standardized assessment protocol by trained ICU nurses who were blinded to group allocation. Patients either had an endotracheal tube or tracheostomy, were aged 18 to 65 years, were mechanically ventilated without receiving neuromuscular blocking agents, and, when supportive airway devices were not fixed for any reason, were unable to report their pain. The Behavioral Pain Scale was assessed through direct bedside observation. Measurements were performed at baseline and repeated at regular intervals during ICU admission, including during routine care procedures and clinical interventions, and the total number of assessments per patient was recorded. Data on analgesic and sedative medication use, including drug type, dosage, and frequency of administration, were collected throughout the study period. These variables were compared between groups and considered in the statistical analysis to control for their potential confounding effects on pain outcomes.
Data were analyzed using SPSS version 26. Data normality was assessed using the Shapiro-Wilk test. Descriptive statistics, including frequency, percentage, mean, and standard deviation, were reported. Inferential analyses and group comparisons were performed using repeated-measures ANOVA, the independent t-test, the Mann–Whitney U test, and correlation analysis. A p-value of < 0.05 was considered statistically significant. Before the inferential analyses, the assumptions of parametric tests were evaluated. Normality was assessed using the Shapiro–Wilk test and an examination of residual distributions. The results indicated no significant departure from normality (p > 0.05), supporting the use of parametric statistical tests, including the independent t-test and analysis of variance (ANOVA). No patients were lost to follow-up during the study period, and complete data were obtained for all participants. Therefore, no missing-data imputation was required. Repeated-measures ANOVA (GLM-RM) was used to assess changes in pain scores over time. The assumption of sphericity was tested using Mauchly’s test. When the assumption was violated, Greenhouse-Geisser corrections were applied to adjust the degrees of freedom. Pairwise comparisons were performed with Bonferroni adjustment.
Results
The intervention and control groups were similar in age, gender, marital status, underlying diseases, mechanical ventilation, and level of consciousness, with no significant differences. No significant between-group differences were observed in the use of analgesic and sedative medications during the study period (p > 0.05) (Table 1).
Before the inferential analyses, the assumptions of parametric tests were evaluated. The Shapiro–Wilk test showed that the residual distribution did not significantly deviate from normality (p > 0.05); therefore, parametric tests were considered appropriate for the data analysis.
To evaluate the effect of the intervention, an independent t-test was used to compare the mean pain index scores across the days of the week. No statistically significant between-group difference in pain scores was observed on days 1 and 2 (P > 0.05). However, from day 3 onward, the intervention group demonstrated significantly lower pain scores than the control group (P < 0.05) (Table 2).
The repeated-measures analysis of variance (GLMRM), considering that pain was measured at seven consecutive time points across two assessment periods, showed a statistically significant difference in pain scores over time. Mauchly's test of sphericity yielded W = 0.83, χ² = 18.64, P = 0.031. Therefore, the Greenhouse–Geisser correction (ε = 0.89) was applied (Table 3).
The results also indicated no statistically significant between-group differences in nighttime pain scores on nights 1 and 2 (P > 0.05). However, from night 3 through night 7, the intervention group showed significantly lower pain scores than the control group (P < 0.05) (Table 4).
The repeated-measures analysis of variance (GLMRM), considering that pain was measured at seven consecutive time points across two assessment periods, showed a statistically significant difference in pain scores over time. Mauchly's test of sphericity yielded W = 0.81, χ² = 20.45, P = 0.021. Therefore, the Greenhouse-Geisser correction was applied (ε = 0.87) (Table 5).
Repeated-measures ANOVA showed significant effects of time and significant time × group interactions for both daytime and nighttime pain scores. Pain scores decreased progressively over the seven-day follow-up period, with greater reductions in the intervention group than in the control group. These findings indicate that the pattern of pain reduction over time differed between the two groups. Although the observed effects were statistically significant, the effect sizes were small (Partial η² = 0.021-0.040), suggesting a modest but consistent intervention effect over time.
|
Table 1. Demographic and clinical characteristics of the intervention and control groups
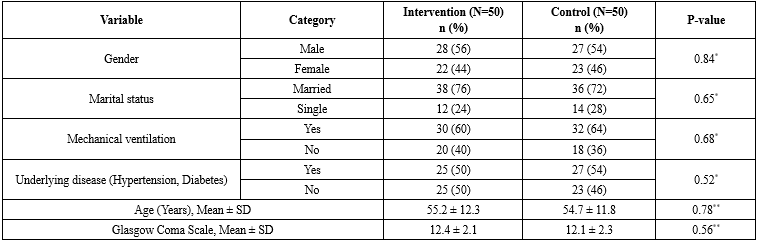 * Chi-Square Test, ** Independent-Samples t-Test, SD= Standard Deviation |
|
Table 2. Daytime pain scores in the intervention and control groups
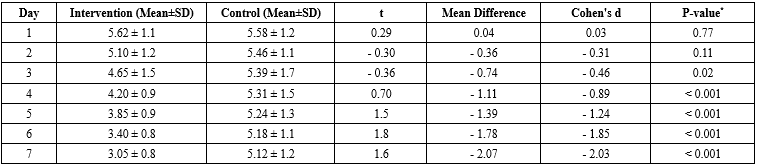 * Independent-Samples t-Test, SD= Standard Deviation Table 3. Repeated-measures ANOVA comparing pain levels from days 1 to 7 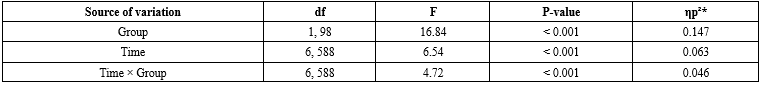 * ηp² = Partial eta squared (Effect size) Table 4. Nighttime pain scores in the intervention and control groups 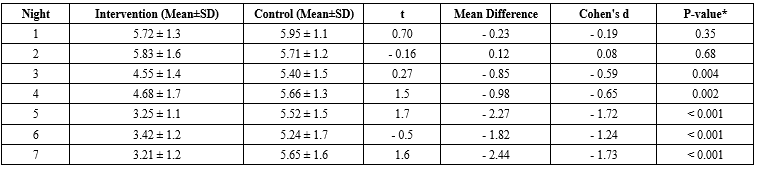 * Independent-Samples t-Test, SD= Standard Deviation Table 5. Repeated-measures ANOVA comparing pain levels from nights 1 to 7 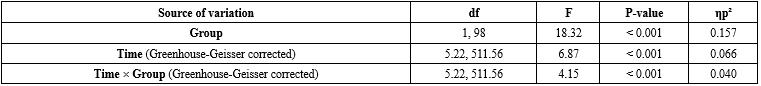 |
Discussion
The present study examined the effect of the Roy Adaptation Model on pain levels among patients admitted to the intensive care unit. The findings indicate that nursing care based on the Roy Adaptation Model may help reduce pain and support patient adaptation in this population.
The experience of pain is often accompanied by fear, anxiety, and stress (14-16). Several non-pharmacological interventions, such as distraction techniques, physical and psychological relaxation, guided imagery, and cutaneous stimulation, provide adaptive strategies that can reduce pain perception and make pain more tolerable (17-19). Previous studies have recommended the Roy Adaptation Model because of its positive and effective impact on patients (20-22). Roy emphasizes that physiological adaptation is one of the key factors contributing to the reduction of disease-related complications (23-25).
The findings of the present study indicated that the intervention was associated with a gradual reduction in pain scores, particularly during nighttime assessments. These results suggest that non-pharmacological pain-relief methods, including nursing care models such as the Roy Adaptation Model, are effective in reducing pain, particularly among ICU patients (26,27). The findings of the present study are consistent with those of Richard-Lalonde et al., who conducted a systematic review and meta-analysis of 18 randomized controlled trials involving adult ICU patients. They reported that music interventions significantly reduced pain intensity, with sessions lasting 20-30 minutes producing the greatest analgesic effect. The authors concluded that music is an effective non-pharmacological adjunct to pain management in critically ill patients (28).
Similarly, Sandvik et al., in a scoping review of non-pharmacological pain interventions in intensive care units, concluded that non-pharmacological nursing interventions can complement pharmacological analgesia by reducing pain, improving patient comfort, and potentially decreasing analgesic requirements. They emphasized that such interventions are safe, inexpensive, and should be integrated into routine ICU nursing care (29).
More recently, Avcı and Kaplan Serin conducted a systematic review of mechanically ventilated ICU patients and found that, across ten studies involving 603 patients, music interventions consistently reduced pain without causing adverse effects. The authors recommended incorporating music as a routine nursing intervention for mechanically ventilated patients because of its safety, feasibility, and effectiveness in pain reduction (30).
The reduction in pain observed in the present study may be explained by the physiological adaptation mechanisms emphasized in the Roy Adaptation Model. Within the physiological mode, nursing interventions focused on improving sleep, nutrition, relaxation, respiratory function, and overall physical stability. These interventions may reduce stress responses, improve physiological resilience, and enhance tissue oxygenation, thereby decreasing pain perception and contributing to the lower pain scores observed in the intervention group.
Therefore, the findings of the present study, together with previous evidence, suggest that the Roy Adaptation Model may reduce pain by improving physiological adaptation. By addressing modifiable physiological needs such as sleep, nutrition, relaxation, and respiratory care, this model may reduce stress responses and improve physiological stability, thereby decreasing pain perception in critically ill patients. These findings support its use as a complementary, non-pharmacological approach to pain management in intensive care units.
Although statistically significant reductions in pain scores were observed, the effect sizes were small (η² = 0.021-0.040), indicating modest intervention effects. Nevertheless, as the Roy Adaptation Model is a safe and low-cost non-pharmacological nursing intervention, even small reductions in pain may be clinically valuable as an adjunct to pharmacological analgesia in ICU patients. However, because analgesic consumption, ICU length of stay, and other clinical outcomes were not assessed, the clinical significance of these findings should be interpreted with caution.
Despite the valuable findings of this study, several limitations should be acknowledged. The study was conducted in a single hospital, which may limit the generalizability of the results to other clinical settings or patient populations. The relatively small sample size may have affected the statistical power of the study. Because patients were unable to self-report, pain assessment was based on observational measures that are inherently subjective and may be influenced by evaluator judgment, individual psychological conditions, level of consciousness, or environmental factors in the ICU. As the study was conducted in a single hospital, contamination between the intervention and control groups may have occurred through interactions among healthcare staff. Sedation level was not assessed using a standardized scale (e.g., RASS), which may have influenced Behavioral Pain Scale (BPS) scores. In addition, the short follow-up period limited the evaluation of the long-term effects of the Roy Adaptation Model-based intervention on pain outcomes. Furthermore, because clinically relevant outcomes such as analgesic requirements, opioid consumption, duration of mechanical ventilation, and ICU length of stay were not assessed, the clinical implications of the observed pain reduction could not be fully determined. Therefore, future studies with larger sample sizes, multicenter designs, and longer follow-up periods are recommended to confirm and extend these findings. The study may have been underpowered to detect small to moderate between-group differences, particularly given the relatively small effect sizes observed. Therefore, the possibility of type II error should be considered when interpreting the non-significant findings across most time points.
Conclusion
The findings of this study suggest that nursing care based on the Roy Adaptation Model, particularly interventions targeting the physiological mode, may be associated with a gradual reduction in pain among patients admitted to the intensive care unit. These findings support the potential value of incorporating theory-based nursing interventions into ICU practice to promote physiological adaptation and improve pain management. However, given the relatively small effect sizes and limited between-group differences observed at individual time points, the findings should be interpreted with caution. If confirmed in future studies, this theory-based approach may provide nurses with a structured framework for planning and delivering individualized pain-management interventions in intensive care settings. Further multicenter studies with larger sample sizes, longer follow-up periods, and more rigorous designs are warranted to confirm the potential effectiveness and generalizability of interventions based on the Roy Adaptation Model in critical care settings.
Acknowledgement
The authors would like to express their sincere gratitude to all intensive care unit nurses for their valuable cooperation and assistance in conducting this study.
Funding Sources
The authors declared that this study received no financial support.
Ethical Statement
This study was conducted in accordance with ethical principles for research involving human participants. All participants provided written informed consent after receiving full explanations of the study objectives, procedures, potential benefits, and risks. For patients with reduced consciousness (GCS≤7), informed consent was obtained from the patient’s legally authorized representative or next of kin. Patient confidentiality was strictly maintained, and the data were used solely for research purposes. The study protocol was approved by the Institutional Research Ethics Board of the University of Lahore (UOL/IREB/26/17/03/04), and all procedures were carried out in accordance with the Declaration of Helsinki.
Conflicts of Interest
The authors have no conflicts of interest to declare.
Author Contributions
Concept: F.A; Design: Sh.S.A; Supervision: Sh.S.A; Resources: A.I; Data collection and/or Processing: S.A; Analysis and/or Interpretation: Sh.S.A; Literature search: R.N; Manuscript writing: Sh.S.A; Critical review: Sh.S.A;
Data Availability Statement
Data will be available upon reasonable request, subject to review by the research team and consideration of data confidentiality.
Use of Artificial Intelligence
No AI tools were used during the preparation of this work.
Type of study: Original Article |
Subject:
Nursing
References
1. Pota V, Coppolino F, Barbarisi A, Passavanti MB, Aurilio C, Sansone P, et al. Pain in Intensive Care: A Narrative Review. Pain Ther. 2022;11(2):359-67. [View at Publisher] [DOI] [PMID] [Google Scholar]
2. Guo N-N, Wang H-L, Zhao M-Y, Li J-G, Liu H-T, Zhang T-X, et al. Management of procedural pain in the intensive care unit. World J Clin Cases. 2022;10(5):1473-84. [View at Publisher] [DOI] [PMID] [Google Scholar]
3. Boncyk C, Rolfsen ML, Richards D, Stollings JL, Mart MF, Hughes CG, et al. Management of pain and sedation in the intensive care unit. BMJ. 2024;387:e079789 [View at Publisher] [DOI] [PMID] [Google Scholar]
4. Zhou T, Wu S, Shi K, Qi X. Incidence and Risk Factors of Chronic Pain After Critical Care Illness: A Systematic Review and Meta-Analysis. Nurs Crit Care. 2026;31(1):e70344. [View at Publisher] [DOI] [PMID] [Google Scholar]
5. Pérez Lucendo A, Piñeiro Otero P, Matía Almudévar P, Alcántara Carmona S, López López E, Ramasco Rueda F. Individualised analgesia, sedation, delirium and comfort management strategies in the ICU: a narrative review. Rev Esp Anestesiol Reanim (Engl Ed). 2023;70(9):509-35. [View at Publisher] [DOI] [PMID] [Google Scholar]
6. Chanques G, Gélinas C. Monitoring pain in the intensive care unit (ICU). Intensive Care Med. 2022;48(10):1508-11. [View at Publisher] [DOI] [PMID] [Google Scholar]
7. Hinkelbein J, Andres J, Böttiger BW, Brazzi L, Robertis ED, Einav S, et al. Cardiac arrest in the perioperative period: a consensus guideline for identification, treatment, and prevention from the European Society of Anaesthesiology and Intensive Care and the European Society for Trauma and Emergency Surgery. Eur J Trauma Emerg Surg. 2023;49(5):2031-46. [View at Publisher] [DOI] [PMID] [Google Scholar]
8. Chen L. Effectiveness of the Roy adaptation model-based nursing intervention in improving physiological, psychological, and social outcomes in patients with Parkinson's disease. BMC Neurol. 2025;25(1):219. [View at Publisher] [DOI] [PMID] [Google Scholar]
9. Hosseini M, Soltanian M. Application of Roy's Adaptation Model in Clinical Nursing: A Systematic Review. J Iran Med Counc. 2022;5(4):540-56. [View at Publisher] [DOI] [Google Scholar]
10. Dayılar Candan H, Doğan S, Güler C, Carroll K. Roy Adaptation Model: Theory-Based Knowledge and Nursing Care With a Person Experiencing COVID-19. Nurs Sci Q. 2022;35(3):304-10. [View at Publisher] [DOI] [PMID] [Google Scholar]
11. Akarsu K. Nursing care after hand replantation based on Roy's adaptation model: A case report. Int J Orthop Trauma Nurs. 2024;52:101039. [View at Publisher] [DOI] [PMID] [Google Scholar]
12. Roussia S, Muthu P, Ilesanmi RE. Self-care Management in Heart Failure Using Roy Adaptation Theory-guided Intervention in the United Arab Emirates. SAGE Open Nurs. 2023;9:23779608231160484. [View at Publisher] [DOI] [PMID] [Google Scholar]
13. Wandrey JD, Behnel N, Weidner E, Dummin U, von Dincklage F, Tafelski S. Behaviour-based pain scales: Validity and interrater reliability of BPS-NI and PAINAD-G on general wards. Eur J Pain. 2023;27(2):201-11. [View at Publisher] [DOI] [PMID] [Google Scholar]
14. Ito Y, Teruya K, Kubota H, Yorozu T, Nakajima E. Factors affecting pain assessment scores in patients on mechanical ventilation. Intensive Crit Care Nurs. 2017;42:75-9. [View at Publisher] [DOI] [PMID] [Google Scholar]
15. Florea R, Linnstaedt SD, Géranton SM. Editorial: Mechanisms underlying the interactions between stress and pain. Front Pain Res (Lausanne). 2023;4:1285257. [View at Publisher] [DOI] [PMID] [Google Scholar]
16. Nakamoto K, Tokuyama S. Stress-Induced Changes in the Endogenous Opioid System Cause Dysfunction of Pain and Emotion Regulation. Int J Mol Sci. 2023;24(14):11713. [View at Publisher] [DOI] [PMID] [Google Scholar]
17. Rijkenberg S, Stilma W, Bosman RJ, van der Meer NJ, van der Voort PHJ. Pain Measurement in Mechanically Ventilated Patients After Cardiac Surgery: Comparison of the Behavioral Pain Scale (BPS) and the Critical-Care Pain Observation Tool (CPOT). J Cardiothorac Vasc Anesth. 2017;31(4):1227-34. [View at Publisher] [DOI] [PMID] [Google Scholar]
18. Shi Y, Wu W. Multimodal non-invasive non-pharmacological therapies for chronic pain: mechanisms and progress. BMC Med. 2023;21(1):372. [View at Publisher] [DOI] [PMID] [Google Scholar]
19. Fan M, Chen Z. A systematic review of non-pharmacological interventions used for pain relief after orthopedic surgical procedures. Exp Ther Med. 2020;20(5):36. [View at Publisher] [DOI] [PMID] [Google Scholar]
20. Ghanbari-Afra L, Yousefizadeh F, Ghanbari-Afra M. An Integrated Review of the Application of The Roy Adaptation Model on Quality of Life, Application of The Roy Adaptation Model on Quality of Life. Journal of Sabzevar University of Medical Sciences. 2023;29(6):811-21 [View at Publisher]
21. Ozdemir O, Unsar S. The effect of education given to hemodialysis patients based on the Roy Adaptation Model on fluid management, symptom control, and quality of life. Nurs Health Sci. 2024;26(2):e13118. [View at Publisher] [DOI] [PMID] [Google Scholar]
22. Chen C-Y, Ding H, Wang S-S. Effectiveness of Roy Adaptation Model-Based Cognitive Stimulation Therapy in Elderly Patients with Non-Small Cell Lung Cancer Undergoing Curative Resection. Tohoku J Exp Med. 2024;263(1):27-34. [View at Publisher] [DOI] [PMID] [Google Scholar]
23. Kim J, Kim H. A Structural Equation Model on Social Re-Adjustment of Stroke Patients: Based on Roy's Adaptation Model. J Korean Acad Nurs. 2023;53(4):480-95. [View at Publisher] [DOI] [PMID] [Google Scholar]
24. Peng Y-N, Jin L, Peng E-J, Zhang L. Perioperative care based on roy adaptation model in elderly patients with benign prostatic hyperplasia: impact on psychological well-being, pain, and quality of life. BMC Urol. 2023;23(1):172. [View at Publisher] [DOI] [PMID] [Google Scholar]
25. Syamsidar S, Asmaningrum N, Rondhianto R. A Systematic Review of Adaptation Measurement Instruments Based on Roy's Adaptation Model in the Nursing Context. JMK. 2025;11(1):248-72. [View at Publisher] [DOI] [Google Scholar]
26. Najafi Ghezeljeh T, Mohades Ardebili F, Rafii F. The effects of massage and music on pain, anxiety and relaxation in burn patients: Randomized controlled clinical trial. Burns. 2017;43(5):1034-43. [View at Publisher] [DOI] [PMID] [Google Scholar]
27. Dağcan N, Özden D, Gürol Arslan G. Pain perception of patients in intensive care unit after cardiac surgery: A qualitative study using Roy's Adaptation Model. Nurs Crit Care. 2024;29(3):512-20. [View at Publisher] [DOI] [PMID] [Google Scholar]
28. Richard-Lalonde M, Gélinas C, Boitor M, et al. The Effect of Music on Pain in the Adult Intensive Care Unit: A Systematic Review of Randomized Controlled Trials. J Pain Symptom Manage. 2020;59(6):1304-19.e6. [View at Publisher] [DOI] [PMID] [Google Scholar]
29. Sandvik RK, Olsen BF, Rygh L-J, Moi AL. Pain relief from nonpharmacological interventions in the intensive care unit: A scoping review. J Clin Nurs. 2020;29(9-10):1488-98. [View at Publisher] [DOI] [PMID] [Google Scholar]
30. Avcı A, Kaplan Serin E. The effect of music on pain in mechanically ventilated patients: A Systematic review. Nurs Crit Care. 2025;30(2):e13270. [View at Publisher] [DOI] [PMID] [Google Scholar]
Send email to the article author
| Rights and permissions | |
 |
This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License. |
